
This site is written from a family-caregiver perspective. The operator is not a medical professional or an insurance, legal or financial adviser. Use this guide to organize questions for the relevant service.
Save the assumptions behind the estimate
Use this follow-up record alongside the guide below. It does not determine medical suitability, insurance eligibility or legal rights, and it does not guarantee a price.
- Keep together
- Procedure description, codes supplied by the office, facility, plan and the estimate’s date and scope.
- Unanswered question
- Is this the applicable contracted amount for the planned service, or a different price measure?
- Next contact and owner
- Ask the insurer and provider to reconcile conflicting descriptions or amounts.
- Recheck when
- The procedure, facility, biller or insurance information changes.
For each response, record its date, source, reference number and what remains uncertain. Agree the next follow-up date instead of treating silence as confirmation. Use official contact channels and keep identifying health, account and policy information out of public comments.

If you have health insurance, the negotiated price for an orthopedic procedure is usually the contracted amount your health plan and a specific provider or facility have agreed to use. The fastest place to look is your insurer’s online price-comparison tool, using the exact procedure code and facility. If the procedure will occur at a hospital, the hospital’s price estimator and public price-transparency file provide a useful second check.
The variable that changes everything is specificity. A price for “knee surgery” or “shoulder injection” is not enough. You need the billing code, the exact facility location, your insurer and plan, and preferably the surgeon or other provider. Without those details, you may find a real price that simply is not your negotiated price.
One more distinction matters before you start: the negotiated rate is not necessarily what you will personally pay. Deductibles, coinsurance, copays, network status, separate professional bills, implants, and other services can change your out-of-pocket cost.
Table of Contents

What “Negotiated Price” Actually Means
For private insurance, a negotiated price generally means a rate established between a health plan or insurer and an in-network provider. Depending on the contract, that rate may apply to an individual service, a group of services, a case, or a formula rather than one tidy retail-style price.
For hospital care, federal Hospital Price Transparency rules require hospitals to publish payer-specific negotiated charges along with other standard charges. Health plans are also subject to separate Transparency in Coverage requirements that make in-network pricing information available and require consumer price-comparison tools for covered services.
That is why two legitimate sources can show numbers that look different. One may show a hospital’s contract rate for a service, while another estimates what your specific plan expects you to owe after applying your benefits.
| Number you see | What it means | Use it for |
|---|---|---|
| Gross charge | Hospital list charge before discounts | Usually not the most useful number for an insured patient |
| Discounted cash price | Price established for patients paying cash or a cash equivalent | Comparing self-pay with insurance |
| Payer-specific negotiated charge | Rate associated with a particular payer or plan | Finding the contract price behind insured care |
| Plan cost estimate | Estimate based on negotiated pricing plus your benefits | Planning your likely out-of-pocket spending |
| Allowed amount on an EOB | Amount recognized when the claim is processed | Verifying the price after care |
Get the Procedure Code Before Looking for a Price
The most useful thing you can obtain from the orthopedic office is not a price. It is the billing information that identifies what is expected to be done.
Ask the scheduler or billing office for the expected CPT or HCPCS code or codes, the exact facility where the procedure will occur, and whether additional procedures are expected. For an inpatient procedure, other coding and payment structures may also matter, so ask whether the estimate is based on an inpatient case, outpatient procedure, or individual service codes.
- Procedure name in plain English
- Expected CPT or HCPCS code
- Any expected modifiers, if known
- Surgeon or treating provider
- Exact hospital, outpatient department, office, or surgery center
- Whether the procedure is expected to be inpatient or outpatient
- Whether an implant, injected drug, imaging, or other major add-on is expected
If unfamiliar billing language starts turning the conversation into alphabet soup, the orthopedic billing terms guide can help you identify which number you are actually being quoted.
Start With Your Health Plan’s Price-Comparison Tool
For an insured patient, the health plan’s own tool is usually the best first stop because it can connect a provider’s negotiated rate with your particular coverage. Under federal Transparency in Coverage requirements, most affected plans and issuers must provide price-comparison information for covered items and services.
CMS explains that these tools are intended to let enrollees compare costs before receiving care and obtain personalized cost-sharing information. You can review the current CMS explanation of health-plan price transparency.
Log in to the insurer or plan portal and search by procedure code when possible rather than relying only on a plain-language procedure name. Then select the exact provider and location. A surgeon may operate at several facilities, and the negotiated amount can change when the site changes.
Save more than the final dollar estimate
Record the date of the search, procedure code, provider, facility, network designation, negotiated or allowed amount shown, and estimated patient responsibility. A screenshot or downloaded estimate gives you something concrete to compare with later information.
Do not treat the tool as a payment guarantee. The actual claim can change if the procedure, coding, site of service, benefits, deductible balance, or services received change.
For Hospital Procedures, Check the Hospital’s Published Prices Too
Hospitals in the United States generally must make standard charge information publicly available. CMS requires a machine-readable file containing hospital standard charges for all hospital-provided items and services, including payer-specific negotiated charges, as well as a consumer-friendly display of shoppable services or a qualifying price estimator.
You can verify the current requirements through CMS Hospital Price Transparency. Hospitals generally must provide consumer-friendly pricing for at least 300 shoppable services, or as many as they provide if they offer fewer.
On the hospital website, look for terms such as Price Transparency, Price Estimator, Standard Charges, or Machine-Readable File. Search using the procedure code, your payer name, your plan name, and the location.
The consumer-facing estimator is usually easier to use. The machine-readable file becomes valuable when the estimator does not show the service, the payer, or enough detail to understand the number.
What changed in hospital price files in 2026
Some hospital contracts do not produce one simple dollar rate because payment is based on a percentage or algorithm. Beginning in 2026, CMS requires additional allowed-amount information in hospital machine-readable files for these arrangements, including the 10th percentile, median, 90th percentile, and the number of allowed amounts used in the calculation.
Those figures can make an opaque contract more informative, but a percentile is still not automatically the exact price for your future claim. Use it as evidence about the payment range and verify your individual estimate with the plan.
The Facility Is Often the Price Hinge
An orthopedic procedure performed in a physician office, hospital outpatient department, or freestanding ambulatory surgery center can involve different contracts and different combinations of charges. Searching only for the surgeon can therefore lead you to the wrong number.
| Setting | Best place to start | Main pricing risk |
|---|---|---|
| Hospital outpatient department | Insurer tool plus hospital estimator | Facility charge may be substantial and separate from physician services |
| Hospital inpatient care | Insurer estimate plus hospital estimate | Case-based or bundled payment may make code-level comparisons incomplete |
| Freestanding surgery center | Insurer tool plus surgery-center estimate | Do not assume hospital transparency files apply in the same way |
| Physician office | Insurer tool plus office billing department | Drugs, imaging, supplies, or other services may be billed separately |
If the hospital portion of the bill is confusing, read the guide to facility fees in orthopedic care. The site of service can matter as much as the procedure itself.
Find Out What the Quoted Price Includes
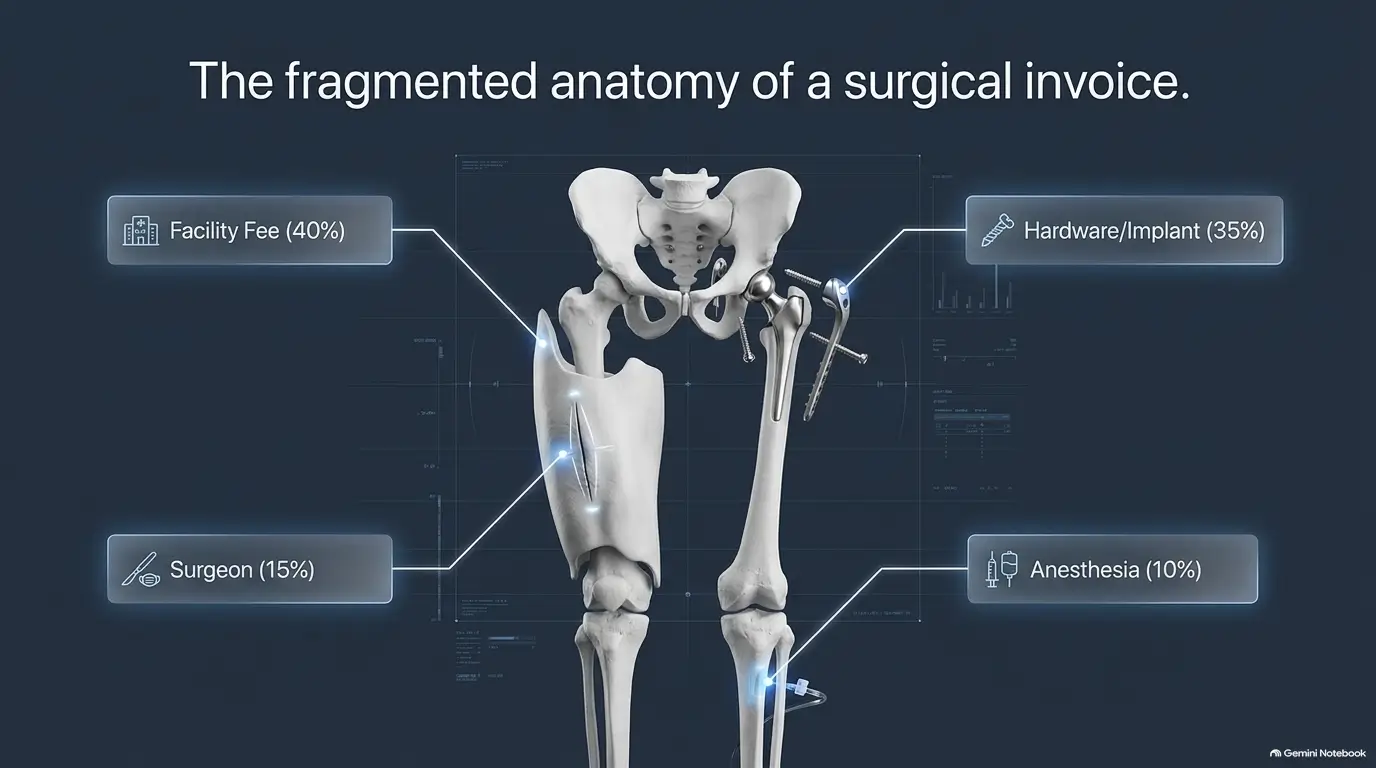
A negotiated facility rate can be accurate and still fail to describe the entire episode of care. Orthopedic procedures often involve multiple entities, and not all of them necessarily share one contract or one bill.
- Surgeon or proceduralist fee
- Hospital or surgery-center facility charge
- Anesthesia services
- Implants or specialized supplies
- Injected medications or biologic products when applicable
- Imaging or image guidance
- Pathology or laboratory services when applicable
- Postoperative visits that are not included in a surgical package
- Physical or occupational therapy
Ask one simple question whenever someone gives you an estimate: “Which providers and services are excluded from this number?”
Anesthesia deserves particular attention because it can appear as a separate professional claim. The separate anesthesia bill guide explains why the surgeon, facility, and anesthesia charges do not always arrive together.
A separate bill is not automatically an unrestricted out-of-network charge. For most private health insurance, the CMS guide to No Surprises Act protections describes limits on unexpected out-of-network bills for non-emergency care related to a visit to an in-network hospital, hospital outpatient department, or ambulatory surgical center. Specified ancillary services, including anesthesiology, cannot use a notice-and-consent form to waive those protections.
This does not make care free or replace your applicable in-network deductible and coinsurance. The federal protection for planned facility care does not apply in the same way at an ordinary physician office or an out-of-network facility, and some coverage types have separate rules. If a professional bill exceeds the insurer’s stated patient responsibility, compare it with the Explanation of Benefits and ask the plan and billing office to review the protection before assuming the full balance is payable. Keep the bill, EOB, and any notice-and-consent paperwork.
Calculate Your Cost From the Negotiated Amount, Not the Sticker Price
Your cost-sharing is normally determined from the plan-recognized or negotiated amount, according to your plan’s rules, rather than simply by taking a percentage of the hospital’s gross charge. Deductible status and the order in which your plan applies cost sharing matter.
Illustrative example: suppose the negotiated facility amount is $8,000, you have $2,000 of deductible remaining, and your plan then applies 20% coinsurance to the remaining covered amount.
- $8,000 negotiated amount
- Minus $2,000 applied to the remaining deductible
- $6,000 remains
- 20% of $6,000 equals $1,200
- Illustrative patient responsibility for that facility claim: $3,200
This example assumes those benefit rules apply exactly as described. It excludes separate surgeon, anesthesia, implant, medication, therapy, imaging, and other possible claims. It also does not account for an out-of-pocket maximum, copays, benefit exclusions, or a different claims-processing sequence.
If you need to build the full pre-surgery number rather than examine one negotiated rate, the orthopedic surgery estimate guide is the better next step.
Compare the Negotiated Rate With the Cash Price Before Paying
Insurance is not automatically the cheapest payment route for every scheduled service. Hospitals also publish discounted cash prices, and other facilities may quote self-pay prices directly. A person with a high deductible may reasonably want to compare both.
Do not compare the cash price only with your estimated insurance payment. Compare the consequences too. Paying outside insurance may mean the spending does not count toward your deductible or annual out-of-pocket limit under your particular plan. Confirm that point with the plan before choosing cash pay.
The cheaper cash option may make sense when the savings are substantial and future deductible accumulation has little value to you. Using insurance may be more rational when you are already near the deductible or out-of-pocket limit, when additional care is likely, or when plan processing provides important protections.
Use This Five-Minute Negotiated-Price Check
Before agreeing to a scheduled orthopedic procedure, put these five pieces of information on one page. This catches most of the expensive mismatches that a vague “What does surgery cost?” question misses.
- Code: Write down the expected CPT or HCPCS code and any known additional procedures.
- Location: Confirm the exact hospital, office, outpatient department, or surgery center.
- Network: Verify the facility and each major professional provider with the health plan, not only with the provider’s office.
- Rate: Save the negotiated rate or plan estimate shown in the insurer tool and compare it with the hospital or facility estimate.
- Exclusions: Ask what is not included, especially anesthesia, implants, medications, imaging, and separate professional fees.
If the procedure requires insurer approval, price verification and authorization should be treated as separate tasks. An authorization does not by itself tell you what the provider will cost or how your benefits will be applied. Use the orthopedic prior authorization checklist if both issues are in play.
When the Published Numbers Do Not Match
A mismatch does not automatically mean one side is wrong. First check whether you are comparing the same code, provider, location, plan, date, and bundle.
Then call the health plan and ask it to identify the in-network negotiated or allowed rate used for its estimate. Ask whether the estimate is based on an individual code, a bundle, a fee schedule, or another payment method. If the hospital file shows a different amount, give the representative the hospital name, location, procedure code, payer, plan, and published figure.
Also verify the date of the hospital file. Hospital standard-charge information must be maintained and updated, but contracts and benefits can change. A number without a date is a much weaker planning tool.
If You Are Not Using Insurance, Ask for a Good Faith Estimate
If you are uninsured or do not plan to use insurance for the service, the task changes. You are no longer primarily searching for your insurer’s negotiated rate. You want the self-pay price and, when applicable, a formal Good Faith Estimate of expected charges.
Under the federal No Surprises Act framework, uninsured or self-pay consumers generally have rights to a Good Faith Estimate for scheduled care or when they request one. CMS explains these protections and the patient-provider dispute process on its Good Faith Estimate and payment-resolution page.
A Good Faith Estimate answers a different question from a payer-negotiated rate. It tells a self-pay patient what a provider or facility expects to charge. If that is your situation, the orthopedic Good Faith Estimate guide is more directly useful than digging through insurer contract data.

FAQ About Orthopedic Negotiated Prices
Why can the same orthopedic procedure have different negotiated prices at the same hospital?
Different insurers and plans can have different contracts with the hospital. The payment method may also vary by plan, and the applicable rate can depend on the location, service package, billing code, or setting. Make sure the payer and plan name match your actual coverage rather than relying on another insurer’s published number.
Is the negotiated rate the maximum I can be charged?
Not necessarily in the sense most patients mean. The negotiated or allowed amount helps determine covered in-network claim payment, but a full episode may generate multiple claims. Your personal liability also depends on deductibles, coinsurance, copays, exclusions, network rules, and other plan terms.
What if I cannot find my orthopedic procedure in the hospital estimator?
Use the hospital’s machine-readable price file and search by billing code, payer, and plan. At the same time, use your insurer’s price-comparison tool. If neither produces a usable result, ask the insurer and facility billing department for a written estimate using the exact procedure code and site of service.
Should I choose the hospital with the lowest negotiated price?
Not from that number alone. First compare your actual estimated out-of-pocket cost and confirm that the surgeon, facility, and major ancillary providers are appropriate for your plan. Clinical suitability, provider qualifications, travel, follow-up care, and the consequences of switching facilities can matter more than a modest contract-rate difference.
Can I negotiate even if I have insurance?
You can ask about payment options, but an in-network provider’s contract may determine how covered services must be billed and processed. If a cash price looks lower, ask both the provider and health plan what happens if you choose self-pay, particularly whether that spending will count toward your deductible or out-of-pocket limit.
Run This Check Before You Schedule
Call the orthopedic office and get the expected procedure code plus the exact facility. Then enter those two pieces of information into your health plan’s price-comparison tool. Save the negotiated rate and estimated patient cost, and compare them with the facility’s own estimate.
If the numbers differ, do not try to solve the discrepancy by guessing which website is “right.” Ask whether the estimates refer to the same code, plan, location, and bundle, and identify which major services are outside the quoted amount. Ten minutes spent matching those details can be more useful than comparing a dozen vague surgery prices.
Targeted update: 17 October 2026. Added the scope and limits of federal surprise-billing protections for separate professional claims, using CMS consumer guidance.
Targeted editorial update: October 21, 2026. Added a topic-specific follow-up record and recheck triggers, revised the title and search description, and removed unverified first-person claims or clarified selected wording where found. The existing body was retained. This update is not a complete legal, coverage or clinical review; confirm current rules and individual decisions with the relevant official source or service.