
Before comparing two orthopedic quotes
A posted hospital charge is not your guaranteed bill. CMS distinguishes public standard-charge data from personal financial responsibility. Use public prices to start questions, then obtain an estimate tied to your planned care and coverage. CMS price transparency FAQ.
| Confirm | Write down |
|---|---|
| Same service | Procedure description, available billing codes, location, inpatient or outpatient setting. |
| Same price type | Patient responsibility, cash price, or negotiated rate. Do not mix them. |
| Same scope | Whether facility, surgeon, anesthesia, and expected related services are included. |
| Same assumptions | Plan, network confirmation, benefit year, quote date, exclusions, and pending questions. |
Caregiver prompt: with the patient’s permission, keep one call log and ask, “What is missing from this estimate, and who should we contact for that part?” Avoid putting policy numbers or patient identifiers into this site’s worksheet. Ask the clinical team whether both sites are appropriate before comparing price.
This guide concerns the U.S. system. Medicare, private insurance, and self-pay processes differ. Check current official guidance and your own plan; do not delay needed urgent care for price shopping. CMS consumer guidance.
Targeted editorial update: October 21, 2026. Added quote-matching and privacy checks, verified against CMS. Other regulatory sections retain their earlier review scope. Written by a family caregiver, not a medical or insurance professional. Our standards.
READER WORKSHEET · USD · Use your own information
Two-hospital patient-cost comparison
Enter written estimates of what you would personally pay, using the same procedure and inclusions.
Enter your quoted amounts
Keep names, account numbers, member IDs, and other identifying details out of this worksheet.
Complete the worksheet to organize your next step. Blank amounts are unknown.
How to use the result: The difference compares entered amounts only. Missing charges, clinical suitability, and insurance terms can change the decision.
This worksheet does not save entries between visits or send them to a provider. Download before leaving; your downloaded file may contain your notes. It is a planning aid, not medical advice, a coverage decision, or a final bill.
Official guidance: CMS medical bill rights · CMS hospital price guidance.

Hospital price transparency can help you compare orthopedic costs before an MRI, injection, arthroscopy, joint replacement, spine procedure, or other scheduled care, but the published hospital price is not necessarily the amount you will pay. For insured patients, the most important number is the plan-specific out-of-pocket estimate after network status, deductible, copay, coinsurance, and out-of-pocket limits are considered. For self-pay patients, the hospital’s discounted cash price and a written good faith estimate matter more.
Start with three facts: the exact procedure or billing code, the planned facility, and whether you will use insurance. Then compare the hospital’s price tool with your health plan’s cost estimator and ask for a written estimate that identifies what is not included. That last step matters enormously in orthopedics because one operation can generate several bills.
Table of Contents

What Hospital Price Transparency Can Tell You Before Orthopedic Care
Federal hospital price transparency rules require covered U.S. hospitals to publish a comprehensive machine-readable file and consumer-facing information for shoppable services. The consumer-facing requirement generally covers at least 300 services, or all applicable services if the hospital provides fewer. A qualifying internet price-estimator tool may satisfy that consumer-facing requirement instead of a separate shoppable-services display; it does not replace the machine-readable file.
For an orthopedic patient, that information may help with scheduled imaging, outpatient procedures, hospital-based surgery, therapy, laboratory services, and other predictable care. CMS explains the patient-facing requirements in its hospital price transparency guidance for consumers.
The published data can include several very different numbers:
- Gross charge: the hospital’s undiscounted charge before discounts or negotiated rates.
- Discounted cash price: the price the hospital has established for patients paying cash or a cash equivalent.
- Payer-specific negotiated charge: the hospital’s negotiated amount for a particular insurer and plan when applicable.
- De-identified minimum and maximum negotiated charges: boundaries showing how negotiated prices vary across payers.
- Additional allowed-amount information: under the 2026 requirements, certain percentage- or algorithm-based arrangements must be represented with specified dollar-based allowed-amount data.
These are useful pricing signals. They are not interchangeable.
The Number You Need Is Your Expected Out-of-Pocket Cost
If you have commercial health insurance, the hospital’s negotiated price is only one ingredient in your bill. What you personally owe can change because of your remaining deductible, coinsurance, copayments, out-of-pocket maximum, network status, coverage rules, and services ultimately performed.
Your health plan therefore deserves equal attention. Most affected group and individual health plans have been required to provide price-comparison information for covered items and services through consumer tools. CMS describes these tools in its Transparency in Coverage consumer guidance.
| Price source | What it tells you | What it may not tell you |
|---|---|---|
| Hospital price estimator | Estimated hospital charge or patient responsibility for a scheduled service | Every independent professional bill or last-minute change in care |
| Hospital machine-readable file | Detailed standard charges and negotiated-price data | Your complete personalized benefit calculation |
| Health plan price tool | Plan-specific estimated cost sharing for a provider or facility | Unexpected services not included in the original search |
| Written hospital estimate | Expected charges for the planned episode as understood at that time | Services billed by entities outside the estimate |
| Good faith estimate for eligible self-pay care | Expected charges from the provider or facility issuing the estimate | A guarantee that no clinical change will alter the services required |
Illustrative example
Suppose your plan’s estimator shows an $18,000 allowed amount for the hospital facility portion of a scheduled procedure. Assume you still have $1,200 of deductible remaining and your plan then applies 20% coinsurance.
- Allowed amount: $18,000
- Remaining deductible: $1,200
- Amount remaining after deductible: $16,800
- 20% coinsurance on that amount: $3,360
- Illustrative facility responsibility: $4,560
That calculation is deliberately simplified. Your actual plan may apply different rules, and an applicable in-network out-of-pocket maximum could reduce what you ultimately owe. Surgeon, anesthesia, therapy, equipment, or other professional charges may also be separate. This is why comparing an orthopedic surgery estimate line by line is more useful than staring at one large hospital number.
Apply the remaining limit before budgeting cash. In a second hypothetical version of the example, suppose the plan confirms that only $1,800 remains to your applicable in-network out-of-pocket limit and all of the illustrated facility cost sharing counts toward it. The $4,560 calculation would then be limited to $1,800 for that claim under those assumptions. If you separately budget $200 for transport that the plan does not cover, the combined cash need is $2,000, not $1,800. These are invented inputs, not a quote.
HealthCare.gov explains what the out-of-pocket limit includes and excludes. Ask the plan to confirm the service, benefit year and current remaining balance. Do not assign the entire remaining limit afresh to every separate claim: claims that count toward the same limit share that balance as they are processed. Keep non-covered household or travel costs in a separate budget.
Why an Orthopedic Procedure Can Produce Several Separate Bills
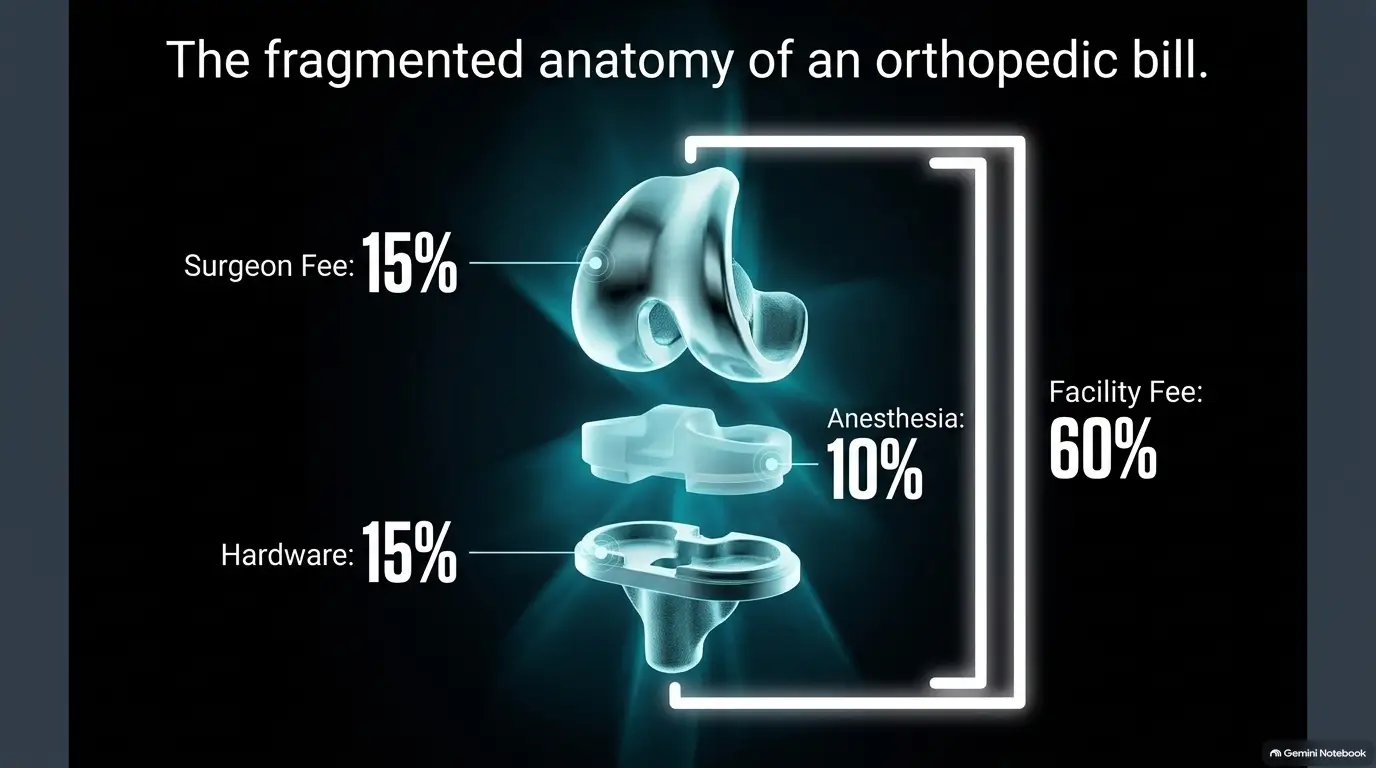
A price that looks like an all-in knee, shoulder, hip, or spine surgery estimate may actually cover only the hospital’s portion. Orthopedic episodes are unusually easy to underestimate because the surgeon, facility, anesthesia group, implant, imaging department, and post-operative services may not all bill through the same entity.
Before accepting an estimate, ask whether it includes each applicable component below:
- hospital or surgical facility charge,
- surgeon’s professional fee,
- assistant surgeon when applicable,
- anesthesia professional services,
- implant, hardware, or device charges,
- imaging and image interpretation,
- laboratory or pathology services,
- inpatient room and board if admission is expected,
- durable medical equipment such as a brace or walker,
- physical or occupational therapy,
- pre-operative testing, and
- follow-up services that are not included elsewhere.
A hospital facility fee alone can materially change the comparison between sites of care. If that part of the bill is unclear, review how a facility fee works in orthopedic care before comparing quotes.
Anesthesia deserves its own question because it may be billed independently. A quoted surgical price should never silently become an assumption that anesthesia is included. A separate anesthesia bill can be legitimate even when the operation itself was scheduled through one hospital.
Run This 10-Minute Price Check Before You Schedule
The most efficient way to use price transparency is to make every source answer the same question. Do not compare a hospital facility price at one location with an all-inclusive patient estimate at another.
1. Get the exact planned service
Ask the orthopedic office for the procedure name, planned CPT or HCPCS code when available, planned facility, and whether the care is expected to be inpatient or outpatient. If more than one procedure may be performed, ask for the likely additional codes too.
2. Search the hospital’s consumer price tool
Search using the procedure description and billing code. Confirm that the result applies to the exact hospital location and setting you will use. Save the date, result, and assumptions shown by the estimator.
3. Run the same service through your insurer
Use the insurer’s cost-comparison tool for the exact facility and surgeon where possible. Look for your estimated responsibility rather than merely the negotiated rate.
Check your current deductible and out-of-pocket accumulators on the same day. An estimate produced early in the year can become stale after another claim changes those balances.
4. Ask the hospital for a written estimate
Give the estimator your insurer, plan information, procedure code, surgeon, and scheduled location. Then ask one deceptively powerful question: “Which charges connected with this procedure are not included in this estimate?”
5. Verify network and prior authorization separately
A low estimate does not prove that the surgeon, facility, or procedure satisfies your plan’s network and authorization rules. Confirm both with the health plan. For scheduled orthopedic care, a structured prior authorization check can help prevent price shopping from overlooking coverage requirements.
6. Save the evidence
Keep PDFs, screenshots, reference numbers, written estimates, and the names or departments involved. Price information is far more useful later when you can show exactly what you were told before treatment.
What Changed in Hospital Price Transparency for 2026
The major 2026 changes affect the detailed machine-readable hospital data more than the basic patient workflow. The consumer-friendly shoppable-services requirement remains important, but CMS tightened how certain hospital pricing arrangements are represented in the underlying file.
Beginning January 1, 2026, hospitals became subject to new requirements for certain payer-specific charges based on percentages or algorithms. Instead of the previous estimated allowed amount approach, the machine-readable file must include median, 10th-percentile, and 90th-percentile allowed amounts plus the number of allowed amounts used for those calculations when the rule applies. Hospitals also have new attestation and organizational NPI requirements. CMS began enforcement of these new machine-readable-file provisions on April 1, 2026.
The CMS summary of the 2026 hospital price transparency changes provides the regulatory details.
For patients, there is a useful but modest takeaway: hospital pricing datasets should contain better standardized evidence of actual allowed amounts in situations where a simple negotiated dollar rate does not exist. That does not mean the median allowed amount is your price, nor does the 10th-to-90th-percentile span predict exactly what your surgery will cost.
Your personal estimate still depends on the exact service, hospital, insurance contract, benefit design, and care actually delivered.
When a Cheaper Site of Care Is Enough
If the same clinically appropriate orthopedic service can be performed at more than one in-network location, comparing sites can be worthwhile. A hospital outpatient department, freestanding ambulatory surgery center, and physician office may have very different billing structures even when a familiar surgeon is involved.
The cheaper option deserves serious consideration when your orthopedic and anesthesia teams consider it medically appropriate, the facility is in network, the necessary equipment is available, and your insurer confirms coverage. Paying more merely because a building carries a hospital name does not automatically buy a better outcome.
Price should stop being the deciding factor when the clinical team believes hospital-level resources, monitoring, inpatient care, or other capabilities are important for your case. Complex revision surgery, significant medical needs, or an expected need for higher-acuity care may change the site decision. That is a clinical judgment, not something a price-comparison tool can settle.
There is another wrinkle: the federal Hospital Price Transparency rule applies to hospitals. A freestanding ambulatory surgery center is not automatically subject to the hospital rule merely because it performs orthopedic surgery. If you are comparing a hospital with a freestanding center, use your health plan’s personalized price tool and obtain estimates directly from both facilities rather than expecting identical public disclosures.
How the No Surprises Act Changes Separate-Bill Risk
An in-network hospital does not necessarily employ every clinician involved in your care. That historically created a nasty billing trap: a patient could choose an in-network facility and later discover that an anesthesiologist or assistant surgeon was out of network.
For health plans and services covered by the federal No Surprises Act, protections generally prohibit out-of-network balance billing and higher out-of-network cost sharing for certain non-emergency services delivered by out-of-network providers at an in-network hospital, hospital outpatient department, or ambulatory surgical center. The protections are particularly relevant to ancillary providers such as anesthesiology and assistant surgeons.
That protection does not make every component of elective orthopedic care free, nor does it make an intentionally chosen out-of-network hospital inexpensive. Your normal in-network deductible, copayment, or coinsurance can still apply. Some non-ancillary out-of-network services can also involve notice-and-consent rules in circumstances permitted by law.
Before scheduled surgery, review CMS guidance on surprise-billing protections for insured patients and ask your insurer to confirm the facility and primary surgeon’s network status.
If You Are Uninsured or Paying Cash, Ask for a Good Faith Estimate
If you are uninsured, or you have insurance but do not plan to use it for the care, a federal good faith estimate can be more valuable than a generic hospital price search. It creates a written record of expected charges for scheduled care from the provider or facility issuing the estimate.
Under current CMS guidance, if qualifying care is scheduled at least three business days in advance, you generally have a right to a good faith estimate. If you ask for an estimate before scheduling, the provider generally must provide it within three business days. Different timing applies depending on how far in advance care is scheduled.
One detail matters especially for orthopedic surgery: a good faith estimate may cover only the provider or facility that issued it. You may receive separate estimates from the surgeon, hospital, anesthesia group, or other providers. Do not assume one document automatically captures the entire episode.
CMS explains the current rules in its good faith estimate guidance. You can also use this orthopedic good faith estimate guide to organize the questions specific to scheduled musculoskeletal care.
If a provider or facility ultimately bills an eligible uninsured or self-pay patient at least $400 more than that provider’s good faith estimate, the patient may qualify for the federal patient-provider dispute resolution process. Eligibility depends on the federal requirements, so keep the estimate and final bill rather than relying on a phone conversation alone.
What to Do If the Final Bill Is Higher Than Expected
Do not begin by assuming either the hospital or insurer made a mistake. First determine whether the difference came from a changed service, a separate provider, an insurance adjustment, or an actual billing problem.
- Compare the bill with the insurer’s Explanation of Benefits. A provider bill should not be analyzed in isolation when insurance was used.
- Request an itemized bill. Look for services, supplies, implants, or departments that were not present in the estimate.
- Match provider names. A second bill may belong to anesthesia, radiology, pathology, or another professional rather than being a duplicate hospital charge.
- Compare procedure codes. Ask why the billed service differs if the final code is not what you priced before care.
- Check your deductible and out-of-pocket balances. Another claim processed before the surgery may have changed your cost sharing.
- Raise surprise-billing concerns promptly. If an out-of-network ancillary provider billed you after covered care at an in-network facility, ask the plan and provider how the No Surprises Act was applied.
If the bill itself is hard to decode, begin with the itemized orthopedic bill rather than negotiating against a single total. The useful question is not simply “Why is this expensive?” It is “Which line or provider created the difference from the pre-service estimate?”
FAQ: Hospital Price Transparency for Orthopedic Patients
Why does my hospital estimator show a different amount from my insurance app?
The tools may be using different data, dates, benefit assumptions, or scopes. The hospital may be estimating its own charges while the insurer is calculating your plan-specific responsibility. Confirm that both estimates use the same facility, procedure, network status, and expected date of service before treating the discrepancy as an error.
Can an insured patient choose the hospital’s cash price instead?
Sometimes a cash price may look attractive, particularly before a large deductible has been met. But paying outside your insurance process may not automatically receive credit toward your deductible or out-of-pocket maximum. Ask the insurer how a self-pay transaction would be treated before choosing cash solely because the posted price is lower.
What happens if the surgeon discovers that more work is needed during the operation?
Pre-service estimates are based on the care reasonably expected at the time. Additional medically necessary procedures, supplies, implants, or longer facility use can change the final claim. Ask before surgery which additional procedures are realistically possible and how they would affect billing, but the clinical team may not be able to predict every intraoperative finding.
Is the hospital’s gross charge useful for comparing orthopedic surgery?
Usually not by itself. The gross charge does not tell an insured patient what the health plan negotiated or what the patient will owe, and it may differ sharply from the hospital’s discounted cash price. It is better used as one reference point than as a forecast of personal cost.
Does Medicare use the same personalized price-comparison process?
Not necessarily. Federal health plan transparency requirements discussed here primarily concern affected private group and individual insurance coverage, while Medicare and Medicaid have their own payment and beneficiary cost-sharing systems. Medicare beneficiaries should verify coverage and expected cost sharing using Medicare and provider-specific information rather than assuming a commercial insurer tool applies.
Your Next 10 Minutes
Find the message, visit summary, or surgical scheduling sheet from your orthopedic office and write down the exact procedure, planned facility, and expected date. Then ask the office for the billing code if it is not already listed.
Run that same procedure through both the hospital and insurer price tools. Save both estimates. Then call the hospital and ask for a written estimate with one sentence at the top of your notes: “Please tell me every expected charge related to this procedure that is not included here.”
That question turns price transparency from a pile of numbers into something useful: a way to find the missing bill before the missing bill finds you.
Last updated: October 15, 2026
Targeted update: 17 October 2026. Added a hypothetical out-of-pocket-limit calculation and separated non-covered spending. Other sections retain their existing review scope.