
This site is written from a family-caregiver perspective. The operator is not a medical professional or an insurance, legal or financial adviser. Use this guide to organize questions for the relevant service.
Resolve the unexplained difference between quotes
Use this follow-up record alongside the guide below. It does not determine medical suitability, insurance eligibility or legal rights, and it does not guarantee a price.
- Keep together
- Facility and setting, same operation, quoted billers, exclusions and estimated patient responsibility.
- Unanswered question
- Is the price difference a real scope-matched difference, or are services missing from one estimate?
- Next contact and owner
- Request an explanation from each issuer and avoid treating an unpriced item as free.
- Recheck when
- Procedure, setting or included services change.
For each response, record its date, source, reference number and what remains uncertain. Agree the next follow-up date instead of treating silence as confirmation. Use official contact channels and keep identifying health, account and policy information out of public comments.

How to Compare Hospital Prices for Knee Replacement
Knee replacement prices can look strangely inconsistent. One hospital may show a cash price, another an insurance-negotiated rate, and a third an estimate that seems to include far more services. Those numbers are not automatically measuring the same thing.
A useful comparison starts by matching the procedure, surgical setting, insurance network and services included. Then compare what you are expected to pay, not merely the hospital’s headline charge.
This guide shows how to turn hospital price-transparency data, insurer estimates and written quotes into an apples-to-apples knee replacement comparison, while keeping quality and surprise bills in view.
The goal is not to find the smallest number on a website. It is to identify the lowest reasonable total cost for the care your surgeon says is appropriate.
Snapshot
This U.S.-focused guide is for patients comparing hospitals or outpatient facilities for a planned knee replacement. Your actual cost can change with insurance, network status, deductible progress, inpatient versus outpatient status and separately billed clinicians. By the end, you should be able to request comparable estimates from two or three facilities and identify which quote deserves a closer look.
Before you act
Price shopping should not determine whether you need knee replacement or whether inpatient, hospital-outpatient or ambulatory surgery is medically appropriate. Those decisions belong with your surgical team. Use this guide after the clinical plan is reasonably clear, and independently confirm coverage, network participation and authorization with your insurer before scheduling.

How Should You Compare Knee Replacement Prices?
Compare knee replacement prices in layers: first confirm the procedure and surgical setting, then check your insurer’s estimate, the hospital’s price estimator, separately billed professional services and finally the facility’s quality data.
Do not begin by comparing hospital chargemaster figures. Federal hospital price-transparency rules require U.S. hospitals to publish standard-charge information and consumer-facing information for shoppable services, but CMS cautions that published standard charges are not necessarily an individual’s out-of-pocket obligation or a guaranteed price.
A practical sequence looks like this:
- Ask the surgeon’s office for the planned procedure and expected setting.
- Confirm which hospitals or surgery centers the surgeon actually uses.
- Check which of those facilities are in your insurance network.
- Run each facility through your health plan’s cost estimator.
- Run the same facilities through their hospital price-estimator tools.
- Request written estimates when the online results are incomplete.
- Ask which professional charges are separate.
- Compare hospital quality and complication information.
If you already have a proposed surgical date, asking for a detailed estimate is usually more useful than browsing hundreds of hospital billing codes. This site’s orthopedic surgery estimate guide can help you identify what should appear on the quote.
A safer way to shop for knee replacement
Same procedure, surgeon plan and care setting.
Compare insurance estimate, hospital estimate and cash option.
Add surgeon, anesthesia and other separately billed services.
Check network, authorization and meaningful quality measures.
What Changes the Price of Knee Replacement?
The answer changes because “knee replacement” is not one identical billing event. Your clinical plan, facility, insurance contract and post-operative needs can all change the financial picture.
The surgical setting
A total knee replacement may be performed in an inpatient or outpatient setting when clinically appropriate. CMS specifically recognizes that total knee arthroplasty can occur on either basis when applicable criteria are met.
That distinction matters because hospital inpatient, hospital outpatient and ambulatory surgical center billing structures are different. Never compare an inpatient estimate from Hospital A with an outpatient estimate from Facility B and conclude that B is simply “cheaper.”
The services bundled into the quote
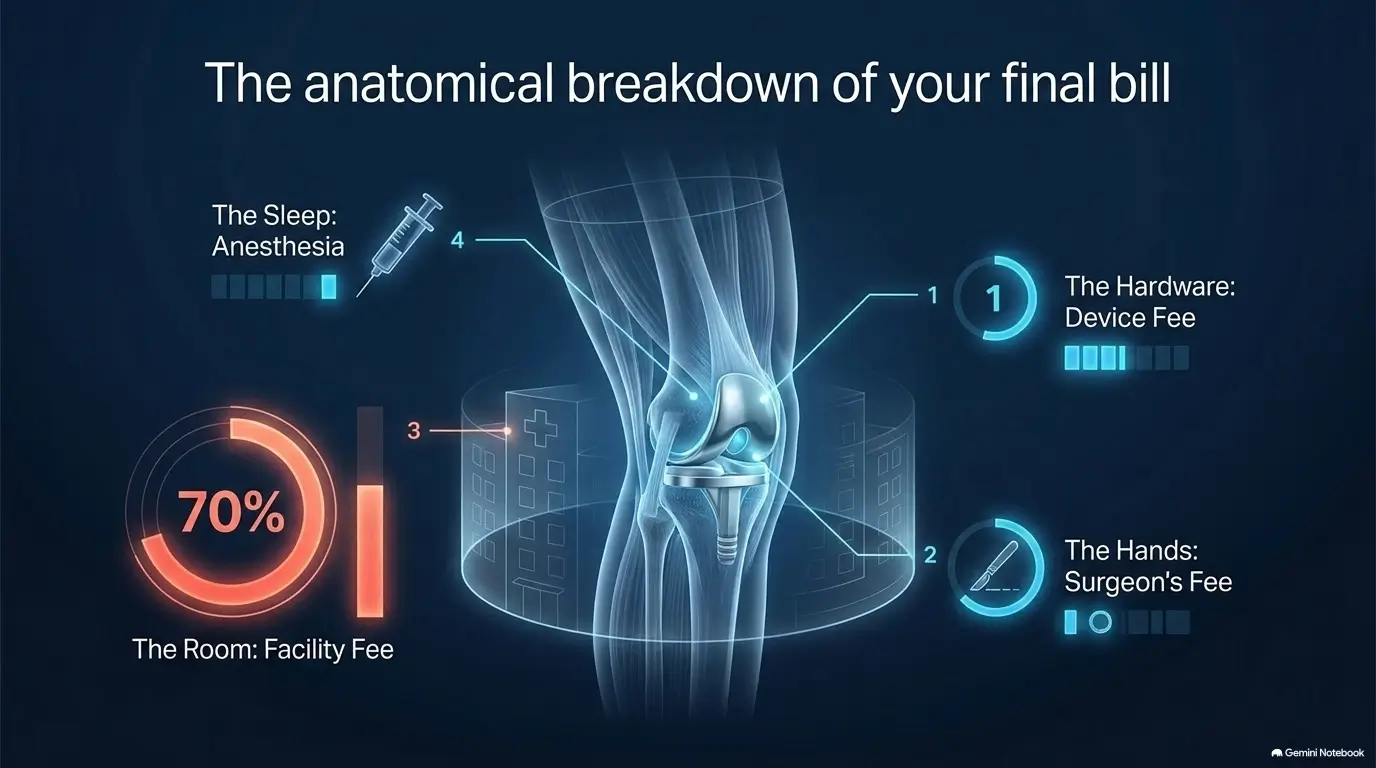
One estimate may include the operating room, implant and routine recovery services but exclude the surgeon or anesthesiologist. Another may combine more components. A smaller number can therefore represent a smaller basket of care.
If the phrase facility fee keeps appearing without a clear explanation, review this site’s guide to facility fees in orthopedic care.
Your insurance contract
Two people having similar surgery at the same hospital can owe different amounts because their plans have different negotiated rates, deductibles, coinsurance, out-of-pocket limits and network rules.
Your medical needs
Additional testing, medical consultations, a longer stay, unexpected treatment or additional post-operative care can change the final bill. An estimate should therefore be treated as a planning document rather than a promise that nothing can change.
Which Hospital Price Actually Matters?
For most insured patients, the most useful number is the estimated amount you personally owe for the planned service at a specific in-network facility. The hospital’s gross charge is generally much less useful for that decision.
CMS requires hospitals to publish comprehensive machine-readable pricing data plus consumer-friendly information for shoppable services. Effective in 2026, CMS also strengthened machine-readable-file requirements around actual allowed-amount information and standardization.
| Price type | What it tells you | Usefulness | What to verify |
|---|---|---|---|
| Gross charge | Hospital’s undiscounted charge | Low for most insured patients | Do not confuse with what you will owe |
| Discounted cash price | Hospital’s self-pay price when applicable | Useful for self-pay comparisons | Exactly what is included |
| Payer-negotiated rate | Rate tied to an insurer or plan | Useful context | Your exact plan and service |
| Hospital patient estimate | Projected patient responsibility | Usually more actionable | Included providers and assumptions |
| Insurer estimate | Plan-specific projected cost sharing | Often the best insured-patient starting point | Network, deductible and authorization status |
Good, Better, Best for price research
Good: use hospital price-transparency pages to narrow a long list of hospitals.
Better: compare hospital estimates for the same procedure and setting.
Best: compare the hospital estimate with your insurer’s personalized estimate, then verify missing professional fees and network status directly.
More expensive research tools are usually unnecessary. For an individual patient, a spreadsheet, the insurer portal and phone calls can be enough. This is one of those rare financial problems where disciplined questions are often worth more than another subscription.
How Do You Build an Apples-to-Apples Comparison?
Give every hospital the same clinical and insurance information and ask the same questions. Otherwise the spreadsheet acquires an impressive number of columns while quietly comparing different things.
Start with the procedure identifier
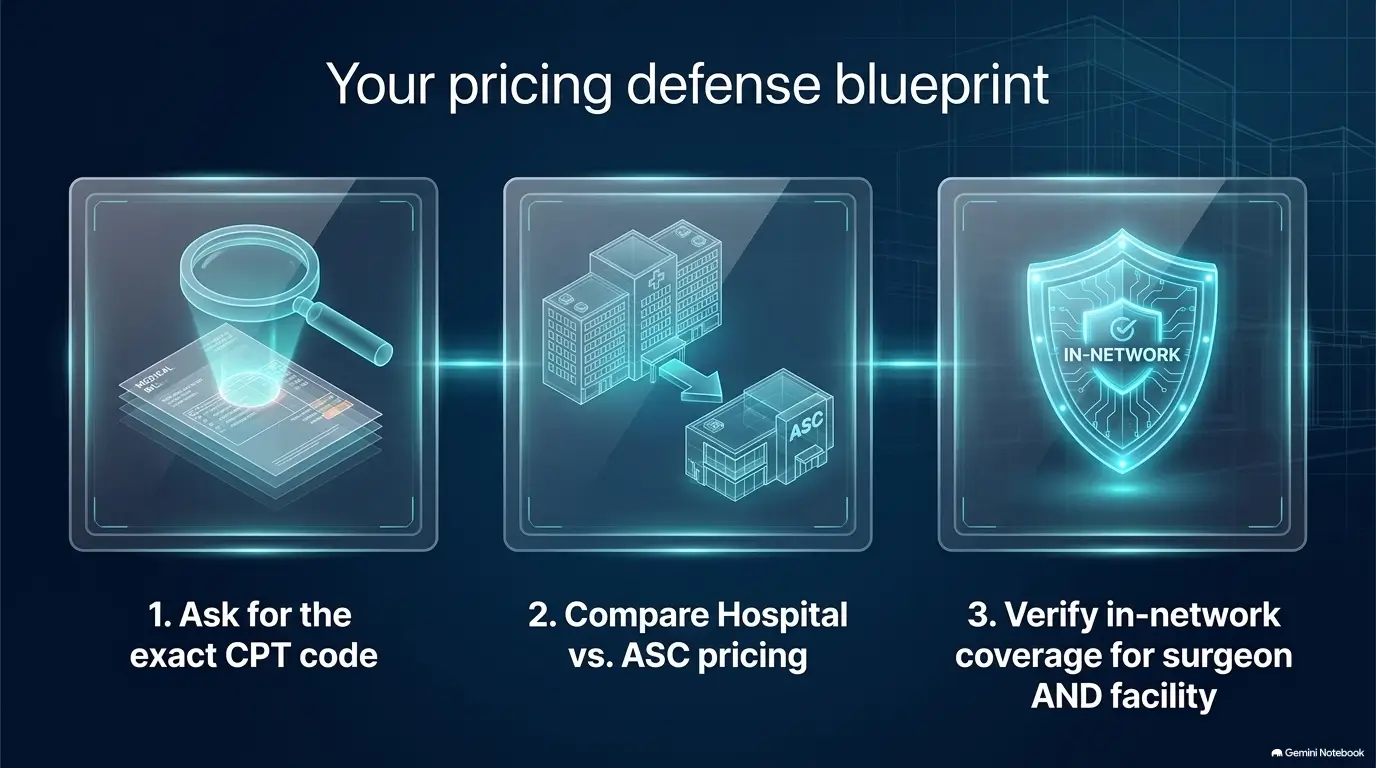
Ask the surgeon’s billing staff what procedure they expect to bill and whether there are likely additional procedures. Medicare’s Procedure Price Lookup currently lists CPT 27447 for primary total knee arthroplasty, but you should not assume that code applies to your particular surgery without confirmation from the surgical office.
For people with Original Medicare, that tool can also provide national average Medicare cost information for procedures available in hospital outpatient departments and ambulatory surgical centers. CMS says the underlying Procedure Price Lookup data are updated annually.
Use this side-by-side worksheet
| Question | Hospital A | Hospital B | Hospital C |
|---|---|---|---|
| In network for my exact plan? | |||
| Inpatient, hospital outpatient or ASC? | |||
| Estimated facility responsibility | |||
| Surgeon included? | |||
| Anesthesia included? | |||
| Total estimated patient responsibility | |||
| Prior authorization confirmed? | |||
| Quality check completed? |
Add the estimate date and the name or reference number from each call. A quote without a date, assumptions or source becomes surprisingly slippery two weeks later.
Use one script with every facility
Hospital estimate script
“I am comparing facilities for a planned total knee replacement. My surgeon expects the procedure to be performed as [inpatient/outpatient, if known]. Can you give me a written estimate using my exact insurance plan and tell me whether it includes the facility, implant, surgeon, anesthesia, imaging, laboratory services and routine recovery care? Please identify anything likely to be billed separately.”
If the hospital gives you only one total, ask for the assumptions behind it. The question “What is missing from this number?” is often more productive than “Is this the final price?”
Technical depth: why one knee replacement can generate several bills
A surgical episode can involve different billing entities. The facility may bill for the operating room, implant, nursing and hospital resources, while the surgeon and anesthesia group may submit professional claims separately. Laboratory, imaging, pathology, therapy or other clinicians can create additional claims depending on the episode.
That is why a facility’s negotiated rate and your total episode cost are not necessarily the same number. Before comparing quotes, identify whether each estimate represents the facility component, a professional component or a broader bundled amount.
Hospital Outpatient vs ASC: Should You Compare Both?
It may be worth comparing a hospital outpatient department with an ambulatory surgical center if your surgeon considers both settings clinically appropriate and both are covered by your plan. Do not change settings simply because one facility appears cheaper.
For Medicare, CMS maintains separate payment information for procedures that can reasonably be performed in hospital outpatient departments and ambulatory surgical centers. Medicare also notes that the amount a beneficiary pays can depend on facility type and where the service is performed.
| Setting | May fit when | Main pricing question | Verify before choosing |
|---|---|---|---|
| Hospital inpatient | The clinical situation supports inpatient admission | What is included in the admission estimate? | Medical necessity, coverage and admission status |
| Hospital outpatient | Outpatient surgery is clinically appropriate | What is the hospital outpatient patient responsibility? | Facility and professional charges |
| Ambulatory surgical center | Your surgeon considers an ASC appropriate | How does total episode cost compare? | Plan participation, surgeon, anesthesia and contingency planning |
How Insurance Changes Your Knee Replacement Cost
If you have private insurance, Medicare Advantage or another managed plan, the hospital’s published price should not be your final coverage check. Your plan determines how its contract, network and benefits apply to you.
Federal Transparency in Coverage rules require most applicable group health plans and individual-market issuers to provide internet-based price-comparison information for covered items and services. For a scheduled procedure, your plan’s member-facing estimator is therefore a sensible first stop.
Ask the insurer these questions
- Is this exact hospital or surgery center in network for my specific plan?
- Is the surgeon in network at that location?
- Is prior authorization required for the knee replacement?
- Does the plan need separate authorization for the facility or inpatient admission?
- What deductible remains?
- What copayment or coinsurance applies?
- What does your system estimate I will owe at each facility?
- Does the estimate include surgeon and anesthesia charges?
- Are there network protections or restrictions for anesthesia and other ancillary clinicians?
- What reference number can I keep for this call?
If authorization is part of the process, use a written checklist rather than assuming the surgeon’s office has completed every payer step. The site’s orthopedic prior authorization checklist is designed for that handoff.
Do not forget separate professional bills
Ask whether anesthesia is included in the hospital estimate and whether you should expect separate professional claims. If you want to map the billing entities before surgery, the guides to orthopedic bills from multiple providers and separate anesthesia billing are useful next steps.
If you are uninsured or intentionally self-paying
Ask each provider or facility for a written Good Faith Estimate before care. CMS says that, in general, people who are uninsured or not using insurance can request a Good Faith Estimate, and scheduled care at least three business days in advance can trigger specific estimate requirements. A single estimate may not capture every provider involved, so surgery patients may need estimates from the surgeon and facility separately.
CMS explains current Good Faith Estimate rules and what the estimate should contain.
If self-pay is your path, this site’s orthopedic Good Faith Estimate guide can help you organize the request.
Under the current federal patient-provider dispute process, qualifying uninsured or self-pay patients may be able to dispute a bill when a provider or facility charges at least $400 more than that provider’s Good Faith Estimate, subject to the program’s requirements and deadline.
How Do You Compare Quality as Well as Price?
Price should narrow your choices, not erase the clinical side of the decision. Once you have two or three financially plausible facilities, compare relevant quality information and discuss the options with the surgeon.
Medicare Care Compare provides hospital quality information, and CMS publicly reports a hip/knee replacement complication measure for applicable hospitals. CMS also has patient-reported outcome reporting related to hip and knee replacement.
Useful questions include:
- Does the surgeon routinely perform knee replacements at this facility?
- Does the hospital publish relevant hip/knee complication information?
- What does the surgeon consider important about each facility’s joint-replacement program?
- How does the facility handle discharge planning and physical therapy?
- If I have significant medical conditions, does that affect which setting is appropriate?
- What happens if an outpatient patient needs a higher level of care?
Price-Comparison Mistakes That Can Cost You
The most expensive mistakes usually happen when a real number is interpreted as the wrong kind of number.
| Mistake | Why it costs money | Safer move |
|---|---|---|
| Comparing gross hospital charges | They may have little connection to your insured responsibility | Compare plan-specific estimates |
| Ignoring the care setting | Inpatient, hospital outpatient and ASC quotes are not equivalent | Match the setting first |
| Assuming “in network” applies to everyone | Surgeon or other clinicians may have separate participation | Verify facility and clinicians |
| Comparing facility-only quotes | Professional bills can sit outside the estimate | Ask what is excluded |
| Skipping prior authorization | Coverage problems can overwhelm a small price difference | Confirm authorization before scheduling |
| Choosing only by price | The lower figure may involve a different or unsuitable care pathway | Compare clinical appropriateness and quality too |
| Failing to save the estimate | You lose the baseline for later billing questions | Keep dated written copies |
Do not compare today’s deductible with yesterday’s estimate
If surgery is several months away, your deductible and out-of-pocket accumulation may change before the procedure. A January estimate and a November estimate can produce different patient-responsibility figures even when the hospital price itself has not changed.
Do not prepay without understanding reconciliation
If a facility asks for payment before surgery, ask whether the amount is a deposit or final expected responsibility, how insurance processing changes it, and how overpayments are refunded. If the expected balance is difficult to manage, ask about financial assistance or a payment arrangement before putting a large charge on high-interest credit. The site’s orthopedic payment plan guide covers questions to ask before agreeing to installments.
When Paying More May Make Sense
Paying more can be reasonable when the higher-cost option solves a real clinical, network or logistical problem. It is not automatically justified because one hospital has a prestigious name or a polished orthopedic wing.
A higher estimate deserves consideration when, for example:
- your surgeon believes one setting is materially more appropriate for your medical needs;
- one facility is in network and the superficially cheaper alternative is not;
- your medical conditions require resources that change the appropriate surgical setting;
- the surgeon’s preferred team or pathway differs in a way that matters clinically;
- one quote is genuinely more complete and the “cheaper” quote is missing major components.
Conversely, paying more may add little value when two options are clinically appropriate, comparably convenient, in network and similar on meaningful quality information, and the estimates truly cover the same episode.
The three-number test
Before choosing, record these comparison figures. Do not automatically add the three totals:
1. Facility estimate: what the hospital expects you to owe.
2. Plan estimate: what your insurer expects you to owe.
3. Missing-services estimate: known charges confirmed to be outside the baseline estimate you intend to use.
If those figures do not roughly reconcile, do not “average” them. Ask why they differ. One may be based on an outdated deductible, a different setting or a different collection of services.
Reconcile overlapping estimates instead of adding every total. In an invented same-plan example, the hospital estimates $2,500 for facility responsibility. A separate surgeon estimate is $600 and anesthesia is $400. If your insurer’s $3,500 estimate already covers all three, the hospital and professional figures reconcile to $2,500 + $600 + $400 = $3,500. Adding the insurer’s $3,500 again would create a false $7,000 budget.
Ask the insurer to identify which billing entities its total includes. Add only amounts confirmed to sit outside the selected baseline estimate, using the same assumptions and current benefit information. A difference between estimates may reflect scope rather than a genuine additional bill; do not use arithmetic to resolve an unknown coverage or billing arrangement.
FAQ
Can I trust the knee replacement price shown on a hospital website?
Use it as comparison information, not automatically as your final bill. CMS notes that hospital standard charges do not necessarily equal an individual patient’s out-of-pocket obligation. Personalized hospital and insurer estimates are usually more useful for the final decision.
Should I compare the cash price even if I have insurance?
You can ask about it, especially if you have substantial cost sharing, but do not assume paying cash is financially better. Confirm whether choosing self-pay would affect claim submission, deductible credit, out-of-pocket accumulation or other plan benefits before making the comparison.
Is the surgeon’s fee included in the hospital price?
Not necessarily. Ask explicitly. Hospital facility charges and professional charges can be billed separately, and anesthesia or other clinicians may also create separate claims.
Can outpatient knee replacement cost less than inpatient surgery?
The financial structure can differ substantially, but the cheaper setting should not be selected independently of medical appropriateness. CMS recognizes both inpatient and outpatient total knee arthroplasty under applicable circumstances, so ask your surgeon which setting is reasonable for you before price shopping.
How many hospitals should I compare?
For many patients, two or three realistic facilities are enough. Comparing ten hospitals is not especially helpful if your surgeon operates at only three and your plan covers only two of them.
What if the insurer and hospital estimates disagree?
Call both and ask what assumptions differ. Check the procedure, care setting, network status, deductible balance, estimate date and whether professional services are included. Keep both written estimates and any call reference numbers.
Do I need a professional medical billing advocate just to compare prices?
Usually not as a first step. A straightforward in-network case can often be compared with insurer tools, hospital estimates and a simple worksheet. Additional help may become more reasonable when there are major out-of-network issues, unusually complex coverage, repeated contradictory estimates or a substantial disputed bill.
Your 15-Minute Knee Replacement Price-Comparison Plan
You do not need to decode an entire hospital database today. Spend the next 15 minutes creating a clean starting point.
- Write down the surgeon’s proposed procedure and setting. If either is unknown, make that your first question for the surgical office.
- List two or three facilities the surgeon uses.
- Open your insurer portal. Confirm which facilities appear in network and save any cost estimates.
- Create three rows in a spreadsheet or note. Record facility, plan estimate, hospital estimate, surgeon included, anesthesia included and authorization status.
- Circle every blank. Those blanks become tomorrow’s phone-call questions.
The useful endpoint: you should be able to say, “These two facilities are clinically reasonable and in network; this is what each estimate includes; this is what my plan thinks I will owe; and these are the remaining unknown charges.” Once you can say that, the fog around hospital pricing has mostly turned into a solvable checklist.
Last reviewed: 2026-09
Targeted review: October 17, 2026. Clarified overlapping facility and insurer estimates with a reconciliation example. Restored 11 table-of-contents links to their heading targets. Other sections retain their stated review scope.
Targeted editorial update: October 21, 2026. Added a topic-specific follow-up record and recheck triggers, revised the title and search description, and removed unverified first-person claims or clarified selected wording where found. The existing body was retained. This update is not a complete legal, coverage or clinical review; confirm current rules and individual decisions with the relevant official source or service.