
This site is written from a family-caregiver perspective. The operator is not a medical professional or an insurance, legal or financial adviser. Use this guide to organize questions for the relevant service.
List what each package omits
Use this follow-up record alongside the guide below. It does not determine medical suitability, insurance eligibility or legal rights, and it does not guarantee a price.
- Keep together
- Same proposed operation, setting, billers, included items, exclusions and payment assumptions.
- Unanswered question
- Are these prices for the same clinical proposal and scope, and who estimates the gaps?
- Next contact and owner
- Get missing component estimates before comparing totals; clinical suitability remains a separate decision.
- Recheck when
- Operation, setting, billers or package terms change.
For each response, record its date, source, reference number and what remains uncertain. Agree the next follow-up date instead of treating silence as confirmation. Use official contact channels and keep identifying health, account and policy information out of public comments.

Orthopedic Surgery Cost Planning
How to Compare Orthopedic Surgery Prices Before Scheduling
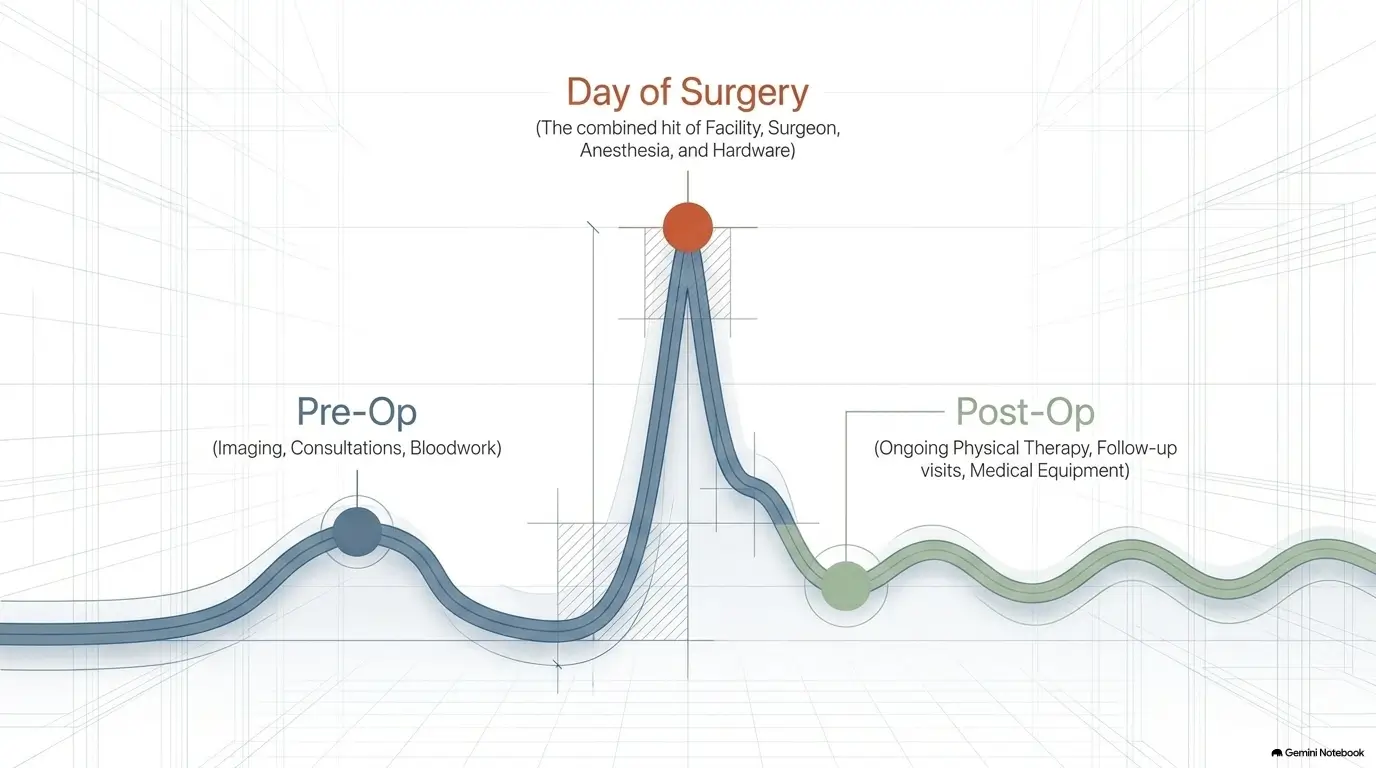
Comparing orthopedic surgery prices is possible, but comparing two numbers from two hospitals is rarely enough. A surgery bill can involve the surgeon, facility, anesthesia, implants or supplies, imaging, pathology, and follow-up services, with different pieces priced or billed separately.
The useful comparison is your expected total out-of-pocket cost for the same planned procedure, at the same type of facility, under the same insurance assumptions. That means collecting a procedure description, expected billing codes when available, facility information, network status, and estimates from more than one party.
This guide shows you how to build that apples-to-apples comparison before choosing a surgery date, while also checking the quieter variables that can turn a tidy estimate into a stack of separate bills.
This U.S.-focused guide is for patients comparing a planned orthopedic operation before scheduling. Your actual cost can change with the procedure, facility, insurer, network, deductible, anesthesia arrangement, surgical findings, and follow-up care. By the end, you should be able to request comparable estimates and identify which questions still need answers.
This article provides general U.S. educational information, not medical or insurance advice. A lower price does not establish that a facility, surgeon, or surgical approach is appropriate for your condition.
Confirm medical suitability with your treating clinicians and confirm benefits, network status, authorization requirements, and estimated cost-sharing directly with your health plan. Do not delay urgent or emergency treatment in order to comparison-shop.
Table of Contents

Can You Really Compare Orthopedic Surgery Prices Before Scheduling?
Yes. For planned surgery, you can often compare meaningful price information before committing to a date. The trick is to compare the same clinical service and the same billing components, rather than treating a hospital estimate, surgeon quote, and insurance calculator as interchangeable numbers.
U.S. hospital price-transparency rules require hospitals to make standard charge information publicly available, while most health plans subject to federal transparency requirements provide members with tools for estimating cost sharing for covered care. These resources can help, but they do not magically assemble every possible bill into one perfect number.
A hospital estimate may focus primarily on the facility. A surgeon’s office may quote the professional fee. An insurer may estimate what you owe based on current deductible information and contracted rates. An anesthesia group may still be a separate participant.
If you are already gathering quotes, the site’s orthopedic surgery estimate guide can help you interpret what an estimate does and does not cover.
Build the Same Surgery Package Before Comparing Prices
Before requesting multiple estimates, get enough information from your surgeon’s office to describe the planned operation consistently. Otherwise you can spend an afternoon comparing numbers that belong to different procedures.
Start with the procedure description
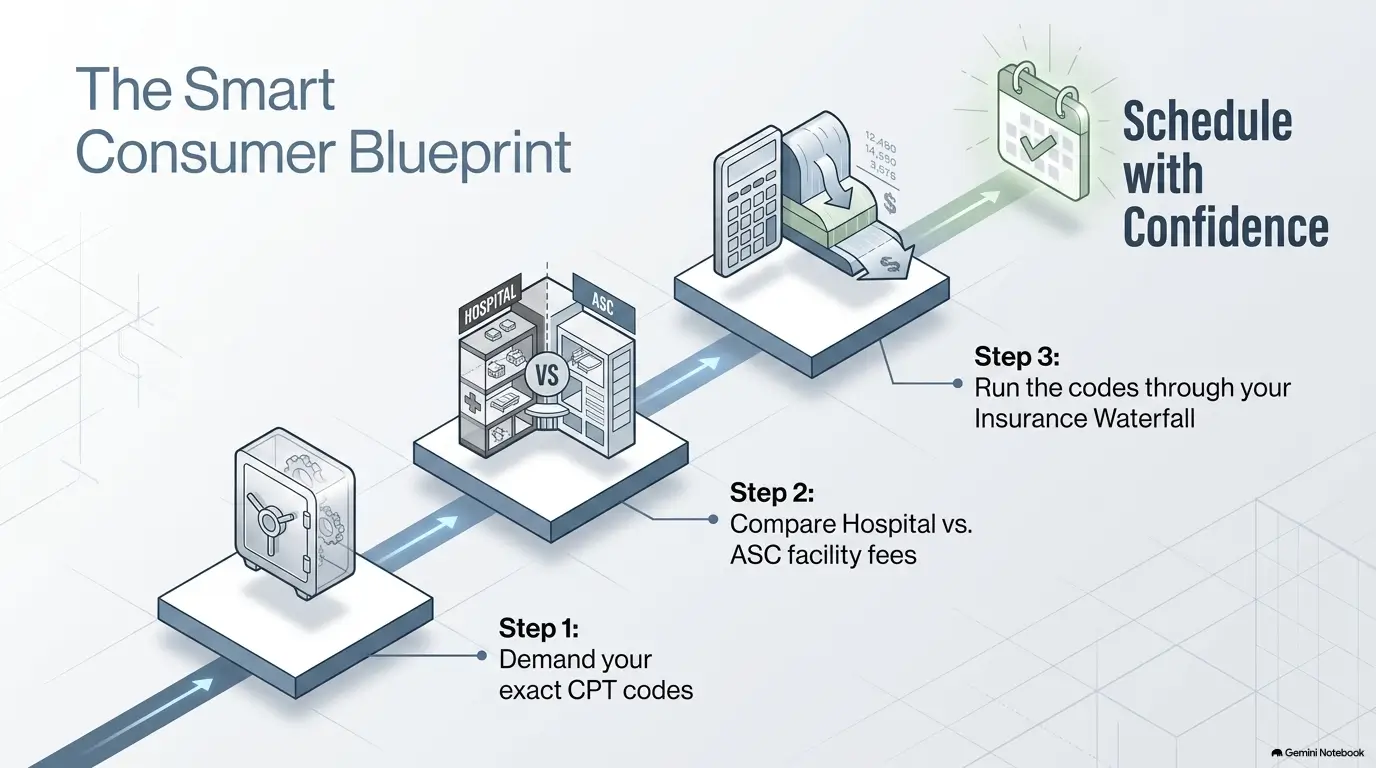
Ask for the exact name of the planned procedure and, when available, the expected CPT or HCPCS procedure code or codes used for estimating purposes. Also ask whether the planned operation may involve an additional procedure depending on what the surgeon finds.
A code is not a promise about the final claim. Surgical findings and clinical circumstances can change what is ultimately performed and billed. Its value during price shopping is that it gives the hospital, insurer, and competing facility a more precise starting point.
Identify the planned site of care
Find out whether the surgery is expected to occur as an inpatient hospital admission, hospital outpatient procedure, or at an ambulatory surgical center. The setting can materially change the facility side of the bill, and not every patient or operation is appropriate for every setting.
If an ambulatory surgical center is medically reasonable for your situation, compare it with the hospital setting rather than assuming that the building is merely a logistical detail. For a deeper look at this distinction, see hospital outpatient vs ASC facility fees.
Write down the likely billing pieces
- Surgeon’s professional services
- Hospital or ambulatory surgery center facility services
- Anesthesia professional services
- Implants, devices, supplies, or medications when applicable
- Assistant surgeon or other professional services when applicable
- Imaging, laboratory, or pathology services when relevant
- Preoperative visits or testing that are scheduled separately
- Postoperative rehabilitation, physical therapy, braces, or equipment when relevant
The point is not to predict every possible line on a future claim. It is to expose the obvious gaps before you compare totals.
Technical depth: why the procedure code alone is not enough
A procedure code can help align estimates, but the final price can also depend on the facility, provider contract, site of care, additional procedures, supplies, anesthesia, and your benefit design.
For a useful comparison, give each estimator the same planned procedure information and ask what assumptions the estimate is making. If one quote includes the facility and surgeon while another includes only the facility, the two totals are not competing prices. They are different slices of the same pie.
How to Compare Facility and Surgeon Prices Without Getting Fooled
Use three sources when possible: the provider or facility estimate, your health plan’s price-comparison tool, and publicly available hospital pricing information. When the numbers disagree, investigate the scope before deciding which one is “right.”
1. Check the hospital’s price estimator
Hospitals subject to federal hospital price-transparency requirements publish standard-charge information and provide consumer-facing information for shoppable care. For a planned orthopedic procedure, search the hospital’s website for “price estimate,” “cost estimator,” or “price transparency.”
CMS maintains current information about these requirements on its Hospital Price Transparency page.
2. Run the same procedure through your insurer
If you plan to use insurance, your plan’s estimate may be more useful than a hospital’s generic sticker price because it can incorporate negotiated rates and your current cost-sharing information. Federal transparency rules require most affected group and individual health plans to provide members with cost-comparison information for covered items and services.
Use the insurer’s logged-in estimator or call the member-services number on your insurance card. CMS explains the consumer tools on its health plan price-transparency page.
3. Ask for estimates from the people who may bill separately
Do not stop after obtaining the hospital estimate. Ask the surgeon’s billing office whether its professional fee is included. Ask whether anesthesia is billed by the hospital, the surgery center, or a separate anesthesia practice.
If the prospect of another envelope arriving three weeks later makes your eyebrow twitch, the guide to a separate anesthesia bill explains why anesthesia deserves its own line on your pre-surgery checklist.
| Source | Best for | Main limitation | What to verify |
|---|---|---|---|
| Hospital estimator | Facility-specific pricing | May not capture every independent professional | Exactly what is included |
| Insurer estimator | Personalized in-network cost sharing | Estimate can change if services change | Network, deductible, authorization |
| Surgeon’s estimate | Professional surgical fee | May exclude facility and anesthesia | Included and excluded services |
| Anesthesia estimate | Separate anesthesia exposure | Final service may depend on clinical needs | Network status and billing group |
An unknown charge is not a zero-dollar charge. For an invented comparison of the same self-pay procedure and setting, suppose option A quotes $8,000 for the facility and $2,000 for the surgeon, with anesthesia still unpriced. Option B quotes $11,500 for those same three components together. A has a $10,000 known subtotal, not a confirmed $10,000 total. You cannot yet conclude that A saves $1,500. Obtain the anesthesia estimate and reconcile any other exclusions before ranking the options.
In your comparison sheet, label each component included, separately priced, or pending. Enter a zero only when you have confirmed that no additional patient charge applies. Record each quote’s date, payment route, and validity terms. Keep incomplete options visible as incomplete; do not turn missing prices into savings or mix a cash package with an insurer’s patient-responsibility estimate.
What Changes Your Out-of-Pocket Cost?
Two patients receiving a similar operation at the same facility may owe different amounts because insurance benefits are personal. Your quoted surgery “price” and your actual financial responsibility are not the same concept.
Your deductible may make the “cheapest hospital” irrelevant
If you have already met much of your deductible or are close to your plan’s out-of-pocket maximum, the difference between two contracted prices may not translate dollar-for-dollar into a difference in what you owe. Conversely, someone early in a high-deductible plan year may feel negotiated-price differences much more directly.
Network status can matter more than the headline price
Confirm the surgeon and facility separately. Then ask about anesthesia and any other known professional groups. Do not assume that everyone working inside an in-network building automatically has the same network relationship with your plan.
Authorization and medical-necessity rules belong in the price check
An attractive estimate is not particularly useful if the required authorization has not been obtained. Before scheduling, confirm who is responsible for submitting authorization and whether approval has actually been received when your plan requires it.
The orthopedic prior authorization checklist can help you organize that conversation.
Cash Price vs Insurance Price: Which Should You Compare?
If you have insurance, compare the expected cost of using it with any legitimate self-pay option rather than assuming that one route is automatically cheaper. The important comparison is not merely “cash price versus negotiated price.” It is your total expected financial responsibility under each route.
Using insurance may make more sense when…
- You have already met a substantial portion of your deductible.
- The surgery will move you materially toward your out-of-pocket maximum.
- The facility and surgeon are in network.
- Your plan covers the procedure and required authorization is in place.
- Postoperative services will also generate covered claims during the same plan year.
A self-pay quote may be worth requesting when…
- You are uninsured.
- You are considering not using insurance for the service.
- Your plan does not cover the service.
- Your deductible exposure makes the contracted route expensive enough that a legitimate cash comparison is useful.
If you are uninsured or choose not to use insurance, federal rules generally entitle eligible patients to a written good faith estimate for scheduled care when the timing requirements are met. Importantly, one estimate may not capture every provider involved, so surgery patients should ask which separate providers or facilities need their own estimate.
CMS explains the current rules and patient protections in its Good Faith Estimate guide.
What to Ask the Surgeon, Facility, and Insurer
A good price comparison is mostly a good question list. Ask for the provider, service, and amount each answer applies to.
Call the surgeon’s billing office
- What is the exact planned procedure?
- Which procedure code or codes are you using for the estimate?
- Which facility is planned?
- Is the surgeon’s professional fee included in the estimate I already received?
- Could an assistant surgeon or another specialist bill separately?
- Who provides anesthesia?
- Are any implants, devices, or special supplies expected?
- What postoperative visits are included in the surgeon’s fee, if any?
Call the facility
- Is this estimate for the facility only or for a bundled group of services?
- Does it include the operating room and expected recovery services?
- How are implants or special supplies treated in the estimate?
- Are anesthesia, pathology, imaging, or other professionals separate?
- Can you send the estimate in writing?
- What could reasonably cause the final amount to increase?
If the words “facility fee” are doing too much work in the conversation, review what a facility fee can mean in orthopedic care before calling back.
Call your insurer
- Is this procedure a covered benefit under my plan?
- Is the surgeon in network for my specific plan?
- Is the facility in network?
- Is prior authorization required, and has it been approved?
- What deductible remains?
- What copay or coinsurance applies to the surgeon and facility?
- What is my remaining out-of-pocket maximum?
- Can you estimate my cost at two or three specific facilities?
- Can you give me a reference number for this call?
Price-Comparison Mistakes That Can Cost You Money
The most expensive mistakes usually come from comparing incomplete numbers, not from failing to discover a secret discount code.
| Mistake | Why it costs money | Safer move |
|---|---|---|
| Comparing different procedures | The quotes are not measuring the same care | Match procedure description and expected codes |
| Comparing facility fee with total surgery estimate | One quote may omit major professional bills | List included and excluded billers |
| Assuming “in network” applies to everyone | Different entities can have different contracts | Verify surgeon, facility, and known separate groups |
| Ignoring authorization | Coverage can depend on plan requirements | Confirm authorization before the procedure |
| Choosing on cash price alone | You may lose the value of insurance cost sharing | Compare total expected out-of-pocket cost |
| Ignoring follow-up care | Rehab and equipment may create additional costs | Map the likely care after surgery |
Another common surprise is the assumption that one hospital bill represents the entire episode. Orthopedic care can involve several billing entities, which is why the guide to orthopedic bills from multiple providers is useful before the paperwork begins multiplying on the kitchen table.
When the Cheapest Option Is Enough and When Paying More Makes Sense
The lowest estimated price can be a perfectly reasonable choice when the medical plan is comparable, the surgeon and facility meet your needs, everyone important is in network, and the lower quote is genuinely complete.
Paying more may be reasonable when the difference buys something clinically or practically meaningful rather than a shinier waiting room.
| Approach | Best fit | Advantage | What to verify |
|---|---|---|---|
| Lowest complete in-network estimate | Comparable routine planned care | Limits unnecessary spending | Same procedure, same scope, adequate quality |
| Higher-cost facility with meaningful advantage | Cases where capabilities or medical needs differ | May better match clinical complexity | Why the higher-cost setting is medically useful |
| Higher-cost surgeon you specifically prefer | Complex cases or meaningful expertise differences | Continuity, experience, or specialized approach may matter | Network consequences and expected total cost |
How to Compare Quality Alongside Price
Price should narrow a decision, not replace the medical decision. A low estimate is useful only if the provider and setting are appropriate for the procedure you need.
For hospitals, Medicare’s Care Compare provides publicly reported information on hospital quality, patient experience, safety-related measures, and other performance information. It will not tell you which surgeon is right for you, but it gives the price spreadsheet a useful companion.
Questions worth asking the surgeon
- Why is this procedure recommended for my condition?
- Are reasonable non-surgical options still available?
- Why is this particular facility appropriate?
- Would a hospital outpatient department or ambulatory surgical center both be medically appropriate for me?
- What complications or medical conditions would make one setting safer than another?
- What should I expect after surgery, including rehabilitation and follow-up?
- If I am considering another surgeon, what records or imaging should I take for a second opinion?
Do not ask a price-shopping tool to answer a medical question. Use the clinical team to assess suitability and the price tools to compare costs.
Frequently Asked Questions
Can I get an orthopedic surgery price before I schedule?
Often, yes. For planned care, you can request estimates from the surgeon and facility and use your insurer’s cost-comparison resources when applicable. The estimate may change if the procedure, site of care, or services ultimately provided change.
Is the hospital’s online price the amount I will actually pay?
Not necessarily. Hospital pricing information may describe facility pricing or standard charges, while your personal responsibility can depend on negotiated rates, deductible status, coinsurance, network status, and other plan rules. Check your insurer’s personalized estimate as well.
Should I ask for the CPT code before comparing prices?
It can help. The planned procedure code gives multiple facilities and your insurer a common reference point. However, codes and services can change if the actual operation differs from what was anticipated, so treat the code as part of the estimate rather than a guarantee of the final claim.
Does the surgery estimate include anesthesia?
Do not assume it does. Ask the facility and surgeon’s office whether anesthesia is included and whether a separate anesthesia practice is expected to bill you.
Should I compare a hospital with an ambulatory surgical center?
It can be worth comparing when your surgeon says both settings are medically appropriate for your operation and health status. Compare the entire expected cost, not facility fees alone, and verify network status for the facility and professionals.
Can paying cash be cheaper than using insurance?
It can happen, but the correct comparison depends on your plan and circumstances. Consider your remaining deductible, coinsurance, out-of-pocket maximum, whether a cash payment will count toward those amounts, and the cost of related care before choosing the self-pay route.
Does an estimate guarantee that insurance will pay?
No. A price estimate is not the same as a coverage determination or authorization. Confirm coverage, network status, and any required prior authorization directly with your health plan.
Your 15-Minute Orthopedic Surgery Price Check
You do not need to solve the entire American medical billing system before lunch. You need enough structure to make the next phone call useful.
- Write down the procedure. Record the planned surgery name, expected procedure code if available, surgeon, and proposed facility.
- Open your insurer’s member portal. Check the surgeon and facility network status and look for the plan’s cost estimator.
- Get one competing facility estimate. Use the same procedure information so you are comparing the same service.
- Circle every missing component. Surgeon? Facility? Anesthesia? Implants? Other professionals? Follow-up?
- Call the number attached to the biggest uncertainty. Do not schedule merely because one screen produced a reassuring number.
Last reviewed: 2026-09
Targeted review: October 17, 2026. Added an incomplete-versus-complete quote example and a method for recording unpriced services. Restored 11 table-of-contents links to their heading targets. Other sections retain their stated review scope.
Targeted editorial update: October 21, 2026. Added a topic-specific follow-up record and recheck triggers, revised the title and search description, and removed unverified first-person claims or clarified selected wording where found. The existing body was retained. This update is not a complete legal, coverage or clinical review; confirm current rules and individual decisions with the relevant official source or service.