
This site is written from a family-caregiver perspective. The operator is not a medical professional or an insurance, legal or financial adviser. Use this guide to organize questions for the relevant service.
Identify the boundary of each estimate
Use this follow-up record alongside the guide below. It does not determine medical suitability, insurance eligibility or legal rights, and it does not guarantee a price.
- Keep together
- Issuer, services included, separate billers, package exclusions and current document versions.
- Unanswered question
- Does this estimate include that component, and could it appear on another statement?
- Next contact and owner
- Reconcile overlapping or omitted lines before adding amounts together.
- Recheck when
- Package scope, clinical plan or billing arrangements change.
For each response, record its date, source, reference number and what remains uncertain. Agree the next follow-up date instead of treating silence as confirmation. Use official contact channels and keep identifying health, account and policy information out of public comments.

What Is Included in a Joint Replacement Estimate?
A joint replacement estimate can look reassuringly precise while covering only part of the care. The number may represent the hospital, the surgeon, or a broader package. Those are very different things.
For hip or knee replacement, the financially useful question is therefore not simply, “What is the estimate?” It is, “Whose charges are included, which services are excluded, and is this my expected out-of-pocket amount or merely an estimated charge?”
This guide shows you how to audit the estimate before scheduling surgery, compare two estimates without comparing apples to operating-room lights, and identify the separate bills that are easiest to overlook.
Table of Contents
What Is Usually Included in a Joint Replacement Estimate?
A useful joint replacement estimate commonly includes some combination of the surgical procedure, facility charges, surgeon’s professional fee, anesthesia, and supplies used during the procedure. The catch is that a single estimate does not necessarily include all of them.
CMS specifically advises uninsured or self-pay patients that a federal Good Faith Estimate should itemize expected charges for scheduled services. CMS also notes that patients undergoing surgery may need estimates from more than one provider or facility, such as the surgeon and hospital.
That distinction matters because joint replacement involves a team rather than one biller. Your orthopaedic surgeon may perform the procedure, but the operating room belongs to a facility, anesthesia may be billed by another practice, and rehabilitation may occur somewhere else entirely.
The core categories to look for
- Surgeon’s professional fee: the surgeon’s work associated with the operation.
- Hospital or ambulatory facility charge: operating-room resources, nursing, recovery space, and other facility services covered by that estimate.
- Anesthesia: anesthesia professional services and, depending on billing arrangements, related facility resources.
- Implant or prosthesis: the artificial joint components and associated surgical supplies, if included in the quoted package.
- Routine medications and supplies during the facility stay: only to the extent they are included in the facility’s estimated charges.
- Preoperative services: sometimes included, but frequently separate.
- Postoperative follow-up: some surgeon services may be treated differently from facility, therapy, imaging, medication, or rehabilitation charges.
If you want a deeper explanation of the difference between a procedural estimate and the eventual bill, see this site’s guide to an orthopedic surgery estimate. The site’s billing library also separately covers facility fees in orthopedic care.
What May Be Missing From the Estimate?
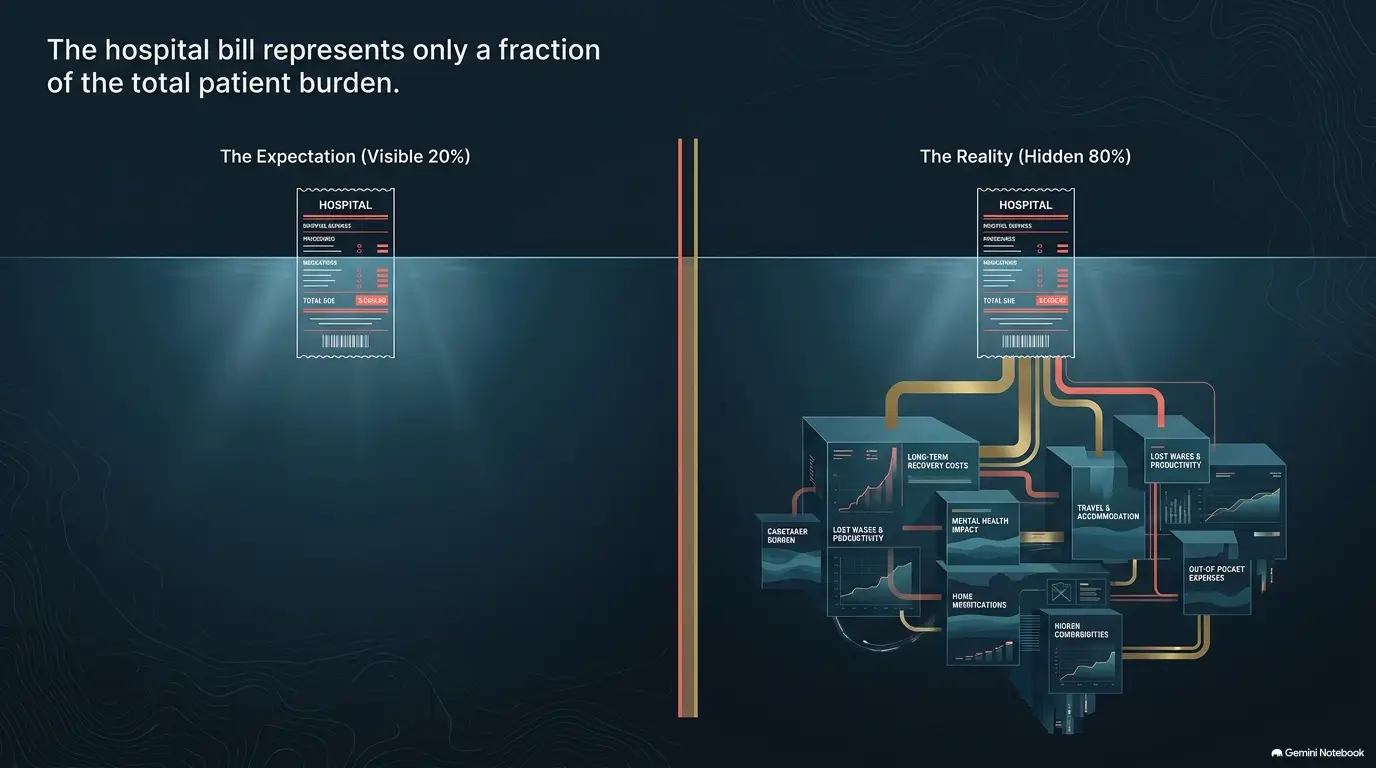
The easiest way to underestimate joint replacement cost is to assume that “surgery estimate” means “everything related to surgery.” It often does not.
Some of the most important exclusions occur before you enter the operating room and after you leave it.
| Possible separate cost | Why it may be separate | What to ask |
|---|---|---|
| Preoperative labs or testing | Performed by another department or provider | Are required pre-op tests included? |
| Imaging | May be ordered or billed separately | Is any pre- or postoperative imaging included? |
| Anesthesia professional fee | Anesthesia group may bill independently | Which anesthesia group is expected to bill me? |
| Assistant surgeon or other clinicians | Separate professional billing may apply | Are additional professional fees anticipated? |
| Physical therapy | Often occurs after discharge under a separate benefit | Is outpatient or home PT included? |
| Home equipment | Walker, mobility, bathroom, or other equipment may be separately obtained | Which items are expected, and who bills them? |
| Home health or rehabilitation | Depends on medical need and discharge plan | Is post-acute care part of this estimate? |
| Prescription medication | May be processed through a pharmacy benefit | Are discharge medications excluded? |
AAOS advises patients preparing for joint replacement to ask in advance about anesthesia, the implant or prosthesis, hospital stay, recovery, and postoperative pain management. Those are not merely clinical questions. They also help reveal which parts of the episode may generate separate charges.
Do not forget the recovery side of the ledger
A remarkably complete operating-room estimate can still tell you almost nothing about what happens after discharge. If your surgeon expects physical therapy, home equipment, home health, or facility-based rehabilitation, ask whether those costs appear anywhere in the estimate.
Planning support can matter financially too. For some households, buying a modest piece of home equipment may be less costly than arranging extra paid help. For others, caregiver availability changes the equation. This site’s comparison of home equipment versus caregiver hours can help frame that separate recovery decision.
What Changes Your Out-of-Pocket Cost?
The total estimated charge and the amount you are likely to pay are not the same number. With insurance, your responsibility can depend on the contracted rate, deductible, copay or coinsurance, network status, benefit design, authorization requirements, and how the claims are ultimately processed.
The answer can also change based on where the operation occurs, which clinicians participate, whether additional services become medically necessary, and whether your coverage changes before the procedure.
What changes the answer?
- Your specific health plan, not simply the insurance company name.
- Whether the surgeon is in network.
- Whether the hospital or ambulatory surgical facility is in network.
- How anesthesia and other professional services will be handled.
- How much of your deductible and out-of-pocket limit you have already satisfied.
- Whether prior authorization or another plan requirement applies.
- The exact planned procedure and surgical setting.
- Whether additional care becomes necessary.
- The expected rehabilitation and discharge plan.
Paying for independent billing or patient-advocacy help may become more reasonable when multiple facilities or out-of-network providers are involved, coverage is disputed, the proposed care is unusually complex, or you cannot reconcile materially different information from the provider and insurer.
How to Read the Facility, Surgeon, Anesthesia, and Implant Charges
When an estimate arrives, read it by billing entity rather than from top to bottom. Four categories deserve particular attention.
1. Facility
The facility portion may cover the operating room, nursing, recovery, hospital resources, and supplies that fall within the hospital or surgical facility’s billing scope. Ask whether the amount is a facility-only estimate and whether the implant is included.
U.S. hospitals are subject to federal hospital price-transparency requirements designed to make standard charge information available to consumers. CMS maintains current information on its Hospital Price Transparency program. Price-transparency information can help you investigate costs, but it should not automatically be treated as your final personal liability.
2. Surgeon
A surgeon’s professional fee is distinct from the facility’s charge. Confirm whether the estimate covers the surgeon only or whether another surgeon, assistant, or clinician is expected to submit a separate professional claim.
3. Anesthesia
Anesthesia is one of the classic places where patients discover another billing entity. Ask for the expected anesthesia group and confirm how your health plan treats that provider. If you are trying to untangle this specific issue, see the guide to a separate anesthesia bill.
4. Implant
Joint replacement uses prosthetic components, but the financial presentation varies. The implant may be incorporated into a facility estimate rather than displayed as a neat retail-style line item.
Ask one simple question: “Is the planned implant included in this amount, and could the estimated patient responsibility change based on the implant selected?” Your surgeon should guide implant selection clinically. Cost is worth clarifying, but it should not replace the medical discussion.
Technical depth: Why can one operation generate several bills?
Insurance vs Self-Pay: Which Estimate Should You Request?
An insured patient and a patient who is not using insurance should not ask exactly the same question. The strongest estimate depends on how the care will be paid.
| Situation | Most useful starting point | Main limitation | Verify next |
|---|---|---|---|
| Using commercial insurance | Provider estimate plus insurer cost-sharing estimate | Claims processing can change the final amount | Network, deductible, authorization, participants |
| Original Medicare | Provider estimate plus Medicare cost information | National averages are not a personal guarantee | Setting, Medicare participation, additional services |
| Medicare Advantage | Provider estimate plus plan-specific estimate | Network and plan rules vary | Authorization, network, cost sharing |
| Uninsured or choosing self-pay | Written Good Faith Estimate from relevant providers/facilities | Unexpected care can still change charges | Which providers are covered by each estimate |
If you are using insurance
Ask the facility for its estimate, but also use your health plan’s cost-estimation resources or call the plan. Federal Transparency in Coverage rules require many group and individual plans to make personalized cost-sharing information available through an online self-service tool or, upon request, on paper.
Do not stop after confirming the surgeon. Ask about the facility and the other professionals expected to participate. Federal surprise-billing protections apply to certain out-of-network services provided in connection with care at in-network hospitals, hospital outpatient departments, and ambulatory surgical centers, but they do not transform every medical bill into an in-network bill.
If authorization is part of your plan’s process, use an orthopedic prior authorization checklist before assuming that an estimate means coverage has been approved.
If you have Original Medicare
Medicare’s Procedure Price Lookup can provide cost information for covered outpatient procedures in hospital outpatient departments and ambulatory surgical centers. Treat it as a comparison tool, not a promise of your exact final bill. Medicare itself notes that additional doctors and costs may apply to procedure estimates.
If you are uninsured or deliberately self-paying
Ask specifically for a Good Faith Estimate, not merely a verbal price range. CMS says that, in most cases, providers and facilities must give uninsured or self-pay patients a Good Faith Estimate when qualifying care is scheduled in advance or when the patient requests one.
If a particular provider or facility ultimately charges at least $400 more than its Good Faith Estimate and the other federal requirements are met, the patient-provider dispute resolution process may be available. Keep the written estimate and every bill.
How to Compare Two Joint Replacement Estimates
Never compare two joint replacement estimates by total alone until you know they describe the same bundle of care.
A $20,000 estimate covering four billing entities cannot intelligently be compared with a $15,000 facility-only estimate. The lower number may be cheaper, or it may simply be wearing fewer clothes.
Use this six-category comparison
| Check | Estimate A | Estimate B | Question |
|---|---|---|---|
| Surgeon | Included? | Included? | Same professional scope? |
| Facility | Included? | Included? | Same setting? |
| Anesthesia | Included? | Included? | Separate group? |
| Implant | Included? | Included? | Same assumption? |
| Pre/post-op services | Included? | Included? | What falls outside? |
| Your responsibility | Estimated? | Estimated? | Same insurance assumptions? |
Short Story: The smaller estimate that was not actually smaller
This is an illustrative scenario, not a documented patient case.
A patient comparing two planned knee replacements receives one estimate with a lower headline number. At first glance, the decision looks easy.
Then the patient asks both offices the same questions. The lower estimate covers the hospital facility only. The second estimate incorporates more of the planned episode, while anesthesia and outpatient therapy are clearly identified as separate.
The first facility has not done anything improper by supplying a narrower estimate. The mistake would be treating two different scopes as interchangeable.
The patient now asks the insurer for personalized cost-sharing information for both options and compares the remaining separate services. The decision is no longer based on which PDF has the smallest number. It is based on which option creates the clearest and most manageable total financial picture.
Costly Estimate Mistakes and the Safer Move
Most estimate problems are not caused by one mysterious charge. They come from comparing mismatched information or assuming that a step has been verified when it has not.
| Mistake | Why it can cost money | Safer move |
|---|---|---|
| Assuming “total” means the whole episode | Separate providers may still bill | Request the list of included billing entities |
| Checking only the surgeon’s network status | Facility or other providers may differ | Verify each expected participant |
| Treating authorization as a price guarantee | Coverage approval and final cost are different issues | Confirm both authorization and cost sharing |
| Comparing sticker charges | They may not reflect negotiated or patient-paid amounts | Compare estimated patient responsibility |
| Ignoring rehabilitation | Therapy or post-acute care may occur outside the surgical estimate | Ask about the expected discharge plan |
| Relying on a phone number alone | It is harder to reconcile later | Ask for the estimate in writing |
| Discarding the estimate after surgery | You lose the easiest comparison with later bills | Save the estimate with EOBs and bills |
If bills later arrive from several organizations, this site’s explanation of an orthopedic bill involving multiple providers is a logical next reference.
Questions to Ask Before You Schedule Surgery
The most useful billing call is not “How much does a knee replacement cost?” It is a short scope audit.
Call the provider and ask
- Is this estimate for the facility only, or does it include professional fees?
- Is the surgeon’s fee included?
- Is anesthesia included? If not, which anesthesia group is expected to bill?
- Is the joint implant included in the estimated amount?
- Are preoperative testing, labs, or imaging included?
- Are routine postoperative visits included in this estimate?
- Are physical therapy, home health, rehabilitation, equipment, and prescriptions excluded?
- Are any assistant surgeons or other separately billing clinicians anticipated?
- Is this amount an estimated total charge or my estimated patient responsibility?
- What could reasonably cause the estimate to change?
Then call your insurer and ask
- Is the planned procedure covered under my current plan, subject to its terms?
- Is prior authorization required, and has it been completed?
- Is the surgeon in network for my exact plan?
- Is the facility in network for my exact plan?
- What should I verify about anesthesia and other professional providers?
- What deductible, copay, or coinsurance is expected to apply?
- How much of my current deductible and out-of-pocket limit has been met?
- Can you give me a personalized cost-sharing estimate for this provider and facility?
- Are outpatient therapy, home health, durable medical equipment, or rehabilitation handled under separate benefits?
If the expected patient share is difficult to manage even after the estimate is clarified, ask the provider about financial assistance or payment arrangements before surgery rather than after bills become overdue. The site’s guide to an orthopedic payment plan covers that next decision.
FAQ
Does a joint replacement estimate normally include the implant?
It may, especially within the facility component, but you should not assume this. Ask whether the planned prosthetic components are included in the estimate and whether implant selection could affect the estimated charges or your responsibility.
Is anesthesia included in a knee or hip replacement estimate?
Sometimes, but anesthesia professional services can be billed separately. Ask which anesthesia group is expected to participate and whether its charges appear in the estimate you received.
Does an estimate include physical therapy after joint replacement?
Do not assume it does. Outpatient therapy, home therapy, home health, or rehabilitation may be separate from the surgery estimate and may be processed under different coverage rules.
Is a surgery estimate the most I can be billed?
Generally, an estimate should not be treated as a guaranteed maximum unless the provider has explicitly offered a contractual arrangement saying so. Actual services, claims processing, and unanticipated care can affect the final bill. Uninsured and self-pay patients receiving a qualifying federal Good Faith Estimate have additional protections when billed charges materially exceed that estimate.
Why is my insurer’s estimate different from the hospital’s estimate?
They may be calculating different things. A hospital may be estimating its charges or the facility portion of your responsibility, while your insurer is applying negotiated rates, deductible status, cost-sharing rules, and plan benefits. Ask both parties to explain the scope behind their number.
Should I compare cash price with my insurance price?
It can be reasonable to ask about both when self-pay is an available option, but compare the complete financial consequences. Paying outside insurance may affect whether the spending is credited toward your deductible or out-of-pocket limit. Confirm this with your plan before choosing based on price alone.
Do I need a medical billing advocate to review my estimate?
Not necessarily. For a straightforward in-network procedure, the provider billing office and insurer may give you enough information at no extra cost. Independent assistance may be more useful when you face unresolved discrepancies, multiple out-of-network issues, denied coverage, or unusually complex billing.
Audit Your Estimate in 15 Minutes
Open the estimate and a blank note on your phone or computer. Your goal is not to decode every billing term. It is to discover what the number does and does not represent.
- Circle the estimated patient responsibility. If you cannot find one, write “unknown.”
- Mark surgeon, facility, anesthesia, and implant. Put “included,” “separate,” or “unclear” next to each.
- Mark pre-op and recovery costs. Check testing, therapy, equipment, prescriptions, home health, and rehabilitation.
- Write down every expected billing organization. If you know only the hospital and surgeon, ask whether others are anticipated.
- Check network and authorization status. Use your exact plan, not a generic provider directory assumption.
- Save the estimate. Put it in the same folder where you will later keep insurer explanations of benefits and medical bills.
Last reviewed: 2026-09
Targeted editorial update: October 21, 2026. Added a topic-specific follow-up record and recheck triggers, revised the title and search description, and removed unverified first-person claims or clarified selected wording where found. The existing body was retained. This update is not a complete legal, coverage or clinical review; confirm current rules and individual decisions with the relevant official source or service.