
This site is written from a family-caregiver perspective. The operator is not a medical professional or an insurance, legal or financial adviser. Use this guide to organize questions for the relevant service.
Do not turn a budget into a therapy prescription
Use this follow-up record alongside the guide below. It does not determine medical suitability, insurance eligibility or legal rights, and it does not guarantee a price.
- Keep together
- Clinician’s plan, provider and location, estimated patient cost, benefit rules and any approved scope.
- Unanswered question
- What changes if the therapist adjusts frequency, visit length, location or services?
- Next contact and owner
- Ask the therapy office and plan to update pricing assumptions when the clinical plan changes.
- Recheck when
- Visit plan, authorization, benefits or provider changes.
For each response, record its date, source, reference number and what remains uncertain. Agree the next follow-up date instead of treating silence as confirmation. Use official contact channels and keep identifying health, account and policy information out of public comments.

Physical Therapy Costs After Joint Replacement: What You May Pay and How to Plan
Physical therapy after a knee or hip replacement can become a meaningful part of your recovery budget, but there is no single reliable “price per recovery.” What you actually pay depends on where therapy happens, how many visits you need, your insurer’s negotiated rate, your deductible and cost-sharing, and whether your recovery requires a higher level of rehabilitation support.
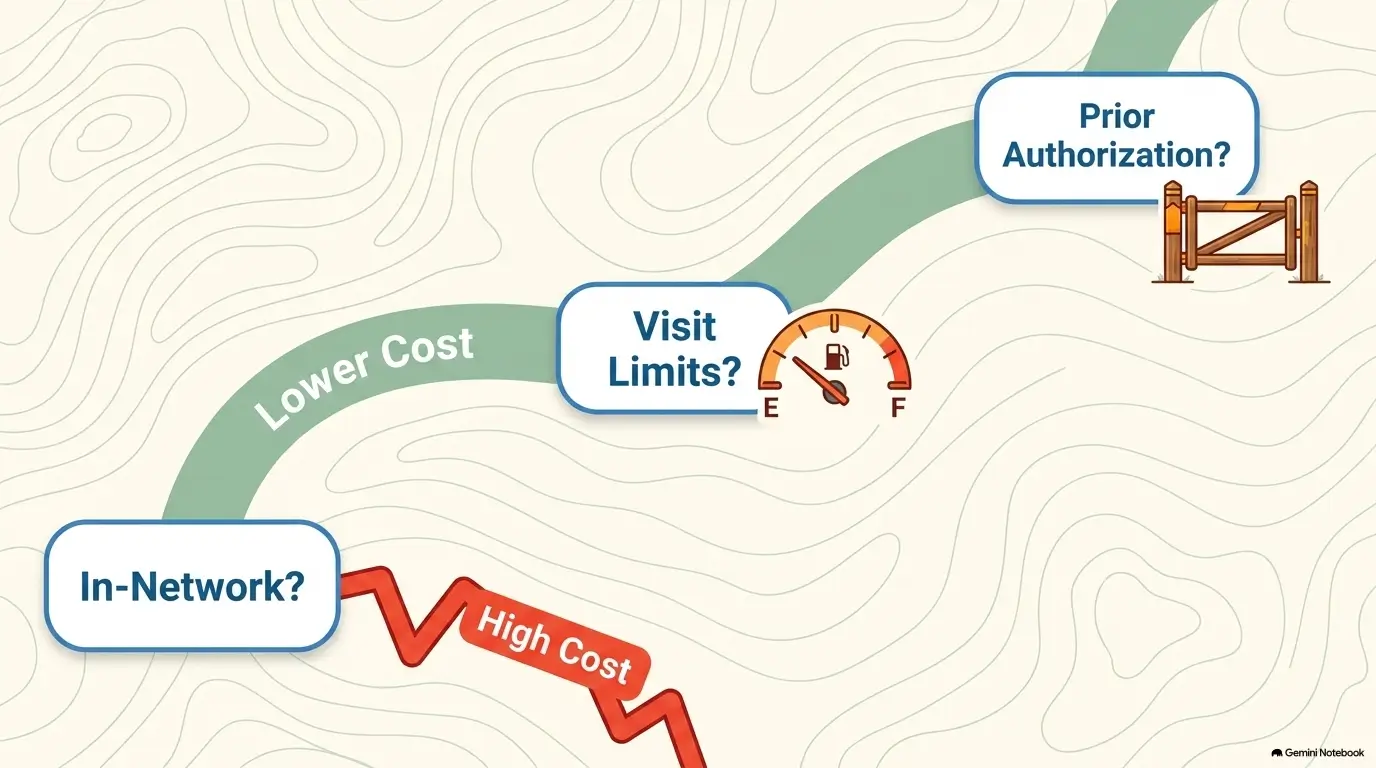
The expensive mistake is often not choosing the “wrong” therapist. It is starting a series of visits without knowing whether the clinic is in network, whether authorization is required, what your benefit charges per visit, or whether a home-based option is appropriate for part of your recovery.
This guide helps you build a realistic physical therapy cost estimate before bills begin arriving, compare outpatient, home-based, and facility rehabilitation, and know when saving money is sensible versus when additional clinical support may be worth the expense.
This US-focused guide is for people planning or receiving rehabilitation after joint replacement. It helps you estimate physical therapy costs without assuming a universal visit price. The biggest variables are your recovery needs, therapy setting, network status, deductible, copay or coinsurance, authorization rules, and number of visits. By the end, you should be able to make a reasonable cost plan and know what to verify before booking.
Physical therapy frequency and exercise progression should be based on your surgeon’s and rehabilitation team’s instructions, not cost alone. A cheaper schedule is not a bargain if it is clinically inappropriate for your recovery.
Contact your clinical team promptly for increasing wound drainage or redness, new calf pain or swelling, or sharply worsening pain. Call emergency services for sudden chest pain or new difficulty breathing after joint replacement; do not wait for the next PT visit or a routine callback.
Table of Contents

How Much Does Physical Therapy Cost After Joint Replacement?
There is no trustworthy universal price for physical therapy after joint replacement. Two people having similar operations can face very different bills because one has a fixed in-network copay while another is working through a deductible and coinsurance.
The number of therapy sessions can also vary substantially. Your surgeon’s protocol, the joint replaced, your baseline mobility, progress after surgery, home support, balance, complications, and functional goals can all change the amount of supervised therapy that is appropriate.
For planning purposes, stop asking only, “How much is physical therapy per visit?” A better question is:
“Given my insurance and expected recovery plan, what is my likely out-of-pocket cost from the first evaluation through discharge from supervised therapy?”
That shift matters because recurring cost-sharing can turn a manageable first visit into a surprisingly large rehabilitation expense over time.
The four numbers you actually need
- Your remaining deductible.
- Your copay or coinsurance for outpatient physical therapy.
- The plan’s allowed amount or estimated patient responsibility for the clinic you intend to use.
- The plausible number and frequency of supervised visits in your current care plan.
You may not know the final visit count on day one. That is normal. Ask your therapist for a planning range and when the plan will be reassessed rather than demanding a false promise of an exact number.
What Changes Your PT Bill After Surgery?
Your total physical therapy expense is shaped by more than the surgery itself. Insurance structure and delivery setting often matter as much as the type of joint replacement.
| Cost driver | Why it matters | What to verify |
|---|---|---|
| Therapy setting | Home health, independent outpatient clinics, hospital-based departments, skilled nursing, and inpatient rehabilitation are paid differently. | Where the service will be billed and under which benefit. |
| Network status | Out-of-network care may have higher cost-sharing or no routine coverage under some plans. | Both the clinic and billing provider. |
| Deductible | You may owe more early in the plan year before insurance begins sharing costs. | How much deductible remains today. |
| Copay vs coinsurance | A copay is usually fixed; coinsurance depends on the allowed amount. | Which applies to PT and whether the evaluation differs. |
| Visit frequency | Recurring cost-sharing compounds quickly. | Expected starting frequency and reassessment points. |
| Authorization | A clinically appropriate visit can still create coverage problems if plan rules were not followed. | Referral, prior authorization, and visit approval rules. |
| Additional services | Equipment, braces, supplies, or separate facility charges may not be included in a simple visit estimate. | What is included and what is separately billed. |
If the terms copay and coinsurance still feel interchangeable, they should not. A fixed copay and percentage-based coinsurance can produce very different total costs across a multi-visit rehabilitation plan. This physical therapy copay vs coinsurance guide explains the distinction in more detail.
What does not reliably tell you the cost
- The clinic’s full billed charge by itself.
- A friend’s PT bill from another insurer.
- Your surgeon’s estimate for the operation.
- A generic web search for “average physical therapy cost.”
- The price of your first visit without considering follow-up care.
Your surgery estimate may not include rehabilitation scheduled separately afterward. Treat postoperative PT as its own cost question.
Outpatient vs Home Health vs Rehab Facility: Which Setting Costs More?
The least expensive clinically appropriate rehabilitation setting is usually the one worth investigating first. But “cheapest” cannot be separated from whether you can move safely, manage daily activities, and complete the recommended program in that setting.
| Setting | Often fits | Cost consideration | Verify first |
|---|---|---|---|
| Structured home program with clinical follow-up | Lower-risk recovery with safe mobility and reliable ability to perform prescribed exercises. | May reduce the number of paid in-person encounters if your clinician considers that appropriate. | What exercises, progression rules, and follow-up schedule are required. |
| Outpatient physical therapy | People able to travel safely who need supervised progression, gait work, strength, mobility, or functional training. | Each visit may trigger copay, coinsurance, or deductible responsibility. | Network, allowed amount, authorization, and estimated visit frequency. |
| Home health rehabilitation | Eligible patients who need skilled care at home and meet payer requirements. | Coverage operates under different rules from ordinary outpatient PT. | Eligibility, agency participation, and what services are covered. |
| Skilled nursing or inpatient rehabilitation | Patients whose medical or functional needs make direct home recovery inappropriate. | Facility benefits, deductibles, daily cost-sharing, and eligibility rules can dominate the cost. | Why facility care is medically recommended and what your plan covers. |
The choice is therefore not simply “home versus clinic.” It is a clinical and financial matching problem. If you are deciding between discharge paths, see this practical guide to choosing rehabilitation after surgery.
Do not pay for a higher-intensity setting merely because it sounds more comprehensive. Do not choose a lower-intensity setting merely because it is cheaper. Ask what level of support your current mobility and medical needs actually require.
How Insurance Changes What You Actually Pay
With private insurance, your patient responsibility may depend on the deductible, copay or coinsurance, network status, authorization rules, plan exclusions, benefit limits, and how the clinic bills the service.
This is why a clinic saying “we take your insurance” is not enough. That phrase does not tell you what your plan will pay, whether the specific location is in network, or what you will owe.
Use this insurance verification script
Call the number on your insurance card or use your plan’s secure portal. Ask:
- Is outpatient physical therapy covered under my current plan?
- Is this exact clinic location and billing entity in network?
- Do I have a deductible for PT, and how much remains?
- After the deductible, do I pay a copay or coinsurance?
- Is the initial evaluation treated differently from later sessions?
- Is a physician referral or prior authorization required?
- Are there visit limits, authorization blocks, or medical-necessity reviews I should know about?
- Could a hospital-owned PT location create different cost-sharing from an independent clinic?
- Where can I see my estimated patient responsibility in writing?
Write down the representative’s name or reference number and the date of the conversation. It will not guarantee claim payment, but it gives you a much cleaner record if the eventual explanation of benefits looks wrong.
Technical depth: billed charge vs allowed amount vs what you owe
A clinic may submit a billed charge that is higher than the amount an in-network insurer recognizes under its contract. The insurer’s negotiated or allowed amount is generally the more useful figure for estimating coinsurance.
If you still have deductible remaining, some or all of the allowed amount may become your responsibility until the deductible is satisfied. After that, a plan may apply a fixed copay or percentage coinsurance according to its benefit design.
This is why multiplying a clinic’s retail price by your coinsurance percentage can produce a misleading estimate. Ask your insurer or clinic for the expected allowed amount or patient-responsibility estimate for your specific plan whenever available.
If medical billing terminology is slowing you down, this orthopedic billing terms guide can help you decode the estimate and explanation of benefits.
Medicare Physical Therapy Costs After Joint Replacement in 2026
Under Original Medicare, medically necessary outpatient physical therapy is generally covered by Part B. In 2026, the Part B deductible is $283, and after the deductible Medicare beneficiaries generally pay 20% of the Medicare-approved amount for covered outpatient physical therapy. Medicare states that there is no annual dollar cap on medically necessary outpatient therapy.
Check Medicare Physical Therapy Coverage
The 2026 Medicare therapy threshold is not a hard coverage cap
For calendar year 2026, CMS sets the KX modifier threshold at $2,480 for physical therapy and speech-language pathology services combined. Once covered therapy expenses reach that threshold, Medicare claims require additional confirmation that continued services are medically necessary and supported by documentation. CMS also retains a $3,000 targeted medical review threshold for PT and speech-language pathology through 2027. These thresholds are not the same thing as an automatic annual therapy limit.
You can review the current rules on the CMS Therapy Services page. For a more focused walkthrough, see the site’s Medicare Part B physical therapy guide.
Home health can follow different Medicare cost rules
Eligible Medicare beneficiaries pay $0 for covered home health services, which can include physical therapy when the home health eligibility and care requirements are met. This does not mean that any therapist who visits your house is automatically covered as Medicare home health care; the service must meet Medicare’s conditions and be provided through the appropriate home health pathway.
For Medicare Advantage, do not assume Original Medicare cost-sharing applies. Advantage plans set their own deductibles, copayments, coinsurance, network requirements, and utilization rules within Medicare requirements, so check your specific plan before scheduling recurring PT.
If you have Original Medicare, ask whether the provider accepts Medicare assignment and whether Medigap or other secondary coverage changes your remaining share. If you have Medicare Advantage, verify the clinic against the Advantage plan’s network rather than assuming Medicare participation alone is sufficient.
How to Estimate Your Total PT Cost Before the First Visit
You cannot know the exact cost of an entire rehabilitation course before anyone sees how you recover. You can, however, create a useful planning range without inventing a price per visit.
Use this simple cost framework
Projected PT out-of-pocket cost = the deductible, copays, and/or coinsurance your plan actually requires for the covered therapy + separate noncovered services or equipment + related travel or caregiver costs, counting each expense once.
Choose the cost-sharing method your plan actually uses. The framework lists possible cost categories; it does not mean every visit incurs a deductible, copay, and coinsurance together. Ask which apply to the evaluation and treatment visits, and whether any apply in combination.
Invented deductible-and-coinsurance example: an evaluation with a $200 allowed amount plus three later visits at $100 allowed each totals $500. With $300 of the same deductible remaining and 20% coinsurance afterward, the patient amount is $300 + 20% × ($500 − $300) = $340. Assume all visits are covered in network and no copay, other claim, separate deductible, or out-of-pocket-limit adjustment applies. Under a different hypothetical plan with a $40 copay for each of those four visits and no deductible or coinsurance for PT, the total would instead be $160. These are alternative plan designs, not charges to add together, actual clinic quotes, or a recommended visit schedule.
If your plan uses a fixed PT copay, the arithmetic is straightforward once you have a plausible visit range. If you pay coinsurance, ask for the estimated allowed amount rather than relying on the clinic’s full charge.
A mini worksheet you can save
| Remaining deductible | ____________ |
| PT copay or coinsurance | ____________ |
| Estimated allowed amount or patient responsibility | ____________ |
| Authorization required? | Yes / No / Confirm |
| Initial visit frequency | ____________ |
| Next reassessment date | ____________ |
| Equipment or separate charges | ____________ |
| Estimated budget range | ____________ |
Self-pay patients should request an estimate in writing
If you are uninsured or choosing not to use insurance, federal Good Faith Estimate protections may apply. CMS says providers generally must provide a written estimate when qualifying self-pay care is scheduled sufficiently in advance or when an eligible patient requests one. A federal patient-provider dispute process may be available when a bill from a provider is at least $400 above that provider’s Good Faith Estimate.
Review CMS Good Faith Estimate Rights
Remember that postoperative physical therapy scheduled separately from the operation may not appear on the estimate for the surgery itself. If you are paying cash, request a separate PT estimate. You may also find this guide to an orthopedic Good Faith Estimate useful when organizing the paperwork.
When the Cheapest Rehab Option Is Enough, and When Paying More Makes Sense
More therapy is not automatically better therapy. The financially sensible target is enough skilled rehabilitation to support safe, meaningful progress, with an appropriate home program between visits.
| Approach | May fit when | Main advantage | Main limitation |
|---|---|---|---|
| Lean supervised plan | Recovery is uncomplicated, home exercise technique is reliable, mobility is safe, and progress is on track. | Reduces unnecessary recurring visit costs. | Requires good self-management and appropriate clinician oversight. |
| Balanced outpatient plan | You benefit from regular reassessment, exercise progression, gait training, or hands-on instruction. | Combines professional feedback with substantial work at home. | Recurring cost-sharing and transportation can add up. |
| Higher-support rehabilitation | Medical complexity, fall risk, significant weakness, limited home help, delayed progress, or functional barriers require closer support. | More intensive monitoring and assistance. | Usually involves greater total resource use and may require stricter coverage criteria. |
The American Physical Therapy Association published an updated 2026 clinical practice guideline for physical therapist management of total knee arthroplasty, reinforcing that postoperative PT planning should be evidence-based and tailored to clinical needs rather than treated as a generic visit package. You can review the APTA total knee arthroplasty guideline page.
When spending less may be perfectly reasonable
Ask whether fewer supervised visits with a strong home program may be appropriate if you are progressing predictably, performing exercises correctly, moving safely, and meeting agreed functional goals. The therapist should make that call with you based on your recovery rather than on a preset package.
When additional support may justify the cost
More frequent or higher-support rehabilitation may be reasonable when safe walking, stairs, transfers, balance, range of motion, strength, wound-related precautions, multiple health conditions, or limited caregiver support make recovery more complicated.
The same principle applies if progress is unexpectedly slow. The answer should not automatically be “buy more visits.” First determine whether the program, diagnosis, pain control, medical status, adherence, or recovery expectations need reassessment.
Pay for the level of skilled support your recovery needs, not the maximum number of visits your insurance happens to allow.
Billing Mistakes That Can Make Rehab More Expensive
Many avoidable PT costs are administrative rather than clinical. A ten-minute verification before the first visit can be worth more than hunting for a slightly cheaper advertised session price.
| Mistake | Why it costs money | Safer move |
|---|---|---|
| Assuming “we accept your insurance” means in network | The clinic may bill your plan without having an in-network contract. | Verify the exact billing entity with the insurer. |
| Confusing a referral with prior authorization | Having a doctor’s order may not satisfy a separate plan approval requirement. | Ask the plan about both requirements explicitly. |
| Using the clinic’s full charge to estimate coinsurance | Coinsurance is often based on the insurer’s allowed amount instead. | Request an allowed-amount or patient-responsibility estimate. |
| Assuming every visit costs the same | Evaluation, treatment mix, facility setting, or benefit processing may differ. | Ask separately about the initial evaluation and routine follow-ups. |
| Assuming surgery pricing includes rehabilitation | PT may be scheduled and billed separately after discharge. | Build a separate rehabilitation estimate. |
| Ignoring the explanation of benefits | Network errors, authorization problems, or incorrect patient responsibility may go unnoticed. | Compare each EOB with the clinic statement before paying. |
| Buying equipment before asking if you need it | Recovery products can accumulate quickly and some may add little value. | Ask your surgeon or therapist what is actually necessary. |
One more trap deserves attention: paying a cash price without understanding the tradeoff. A clinic’s self-pay rate can sometimes be attractive, but a service paid outside your insurance may not count toward your deductible or out-of-pocket accumulation. Verify that consequence before deciding that cash is cheaper overall.
What to Ask a Physical Therapy Clinic Before You Schedule
A good clinic should be able to explain how it bills, what services are included, and whom you should contact for cost questions. It may not be able to guarantee what your insurer ultimately pays, but it should not make basic billing information feel mysterious.
Ask the billing desk
- What legal entity will bill my insurance?
- Is this exact location in network with my plan?
- Can you estimate my responsibility for the initial evaluation?
- Can you estimate a typical follow-up patient’s responsibility under my plan?
- Do you obtain prior authorization, or is that my responsibility?
- Are there separate facility, equipment, or supply charges?
- What is the cancellation or missed-appointment policy?
- If I self-pay, can I receive a written estimate before treatment?
Ask the therapist
- What are our first functional goals?
- What would make you increase or decrease visit frequency?
- Which parts of rehabilitation should I be doing independently at home?
- When will you formally reassess whether supervised visits are still needed?
- What would make you contact my surgeon or recommend medical reassessment?
- Which equipment, if any, is genuinely necessary?
These questions turn rehabilitation from an open-ended series of appointments into a plan with goals, checkpoints, and financial visibility.
When Your Recovery Plan Needs Reassessment, Not More Visits
If physical therapy does not seem to be helping, the first response should not automatically be to stop therapy or double the number of visits. A plateau can have different causes, and the right next step depends on what is actually limiting recovery.
Useful questions include whether pain is preventing participation, whether the home program is being completed correctly, whether swelling or another postoperative issue is limiting function, whether goals remain appropriate, and whether the surgeon needs to reassess the joint.
You can use this guide on what to do when physical therapy is not helping orthopedic pain to prepare that conversation.
Signs that a cost conversation should become a clinical conversation
- Your function is getting worse rather than merely improving slowly.
- Pain changes substantially or prevents you from participating in rehabilitation.
- You develop new swelling, wound concerns, or other postoperative symptoms.
- You cannot safely complete the home program.
- You repeatedly miss functional goals despite following the plan.
- Your therapist believes progress is inconsistent with the expected recovery course.
Saving money matters. Protecting the result of the operation matters more. Cost planning should help you remove waste, not pressure you into ignoring a recovery problem.

Frequently Asked Questions
How many physical therapy visits will I need after joint replacement?
There is no responsible universal visit count. The appropriate number depends on the joint and procedure, your baseline function, progress, home support, safety, clinical goals, complications, and your surgeon’s and therapist’s plan. Ask for an initial range and a reassessment date rather than an exact promise.
Does insurance usually cover physical therapy after knee or hip replacement?
Many health plans cover medically necessary rehabilitation, but your actual coverage can depend on network participation, deductible, copay or coinsurance, authorization, referral rules, visit limits, and plan-specific medical-necessity criteria. Confirm your own benefits before recurring visits begin.
Is home physical therapy cheaper than outpatient PT?
Not necessarily. “PT at home” can refer to different arrangements with different payment rules. Medicare-covered home health, private home visits, and a home exercise program with outpatient follow-up are not financially equivalent. Compare the actual benefit pathway rather than the address where therapy occurs.
Can I do physical therapy on my own to save money?
A prescribed home exercise program is commonly part of rehabilitation, but replacing supervised therapy entirely may or may not be appropriate. Ask your therapist which activities you can safely manage independently and what milestones require professional reassessment.
Does Medicare stop paying for PT after a certain dollar amount?
Original Medicare does not impose an annual dollar cap on medically necessary outpatient therapy. In 2026, however, claims above the $2,480 PT-and-speech combined KX threshold require appropriate documentation and use of the KX modifier, and higher spending can enter Medicare’s targeted medical-review framework.
Should I choose a cash PT price instead of using insurance?
Compare both paths before deciding. A cash price can be attractive, particularly with a high deductible, but paying outside your plan may mean the expense does not count toward your deductible or out-of-pocket totals. Ask both the clinic and insurer how each option will be treated.
Can the initial PT evaluation cost more than later appointments?
It can. The evaluation and subsequent treatment visits may involve different services and benefit processing. Do not assume one quote applies to every appointment; ask separately about the first visit and expected follow-ups.
Your 15-Minute PT Cost Check Before You Book
You do not need a spreadsheet worthy of an insurance actuary. Fifteen focused minutes can answer most of the questions that prevent avoidable billing surprises.
- Minutes 1–5: Check your insurer. Confirm the exact clinic is in network, your remaining deductible, PT copay or coinsurance, and whether authorization is required.
- Minutes 6–10: Call the clinic. Ask for an estimate for the evaluation and routine follow-ups, whether any facility or equipment charges are separate, and who handles authorization.
- Minutes 11–15: Set a planning range. Write down the therapist’s expected starting frequency, your next reassessment point, and what one week or one month of that schedule could mean for your household budget.
Then keep the estimate flexible. Recovery after joint replacement is not a subscription you should keep renewing on autopilot. As function improves, the plan should be reassessed clinically and financially.
“What am I paying for at this stage that I cannot safely and effectively do on my own, and what milestone will tell us the current visit frequency can change?”
Last updated: October 14, 2026
Targeted review: October 17, 2026. Clarified the possible cost categories and added two alternative cost-sharing calculations. Restored 12 table-of-contents links to their heading targets. Other sections retain their stated review scope.
Targeted editorial update: October 21, 2026. Added a topic-specific follow-up record and recheck triggers, revised the title and search description, and removed unverified first-person claims or clarified selected wording where found. The existing body was retained. This update is not a complete legal, coverage or clinical review; confirm current rules and individual decisions with the relevant official source or service.