

Medicare Part B physical therapy questions are easier to follow when the clinical plan, certification, threshold processing and estimate conditions stay separate. An appointment is not a coverage decision; a threshold is not a visit allowance; an estimate is not the final amount owed. Keep the real answer to each question with its source and date.
Start with the six essential checks, compare what the 2026 thresholds mean, read two fictional writing examples, or use the Medicare PT question and actual-answer record. This page focuses on Medicare-specific conditions and follow-through rather than repeating a general PT cost calculator.
Do not wait for coverage paperwork when urgent care is needed. With back pain, new bladder or bowel changes, loss of feeling around the genitals or anus, or pain, weakness, tingling or numbness in both legs need emergency assessment. Sudden severe joint pain with swelling, heat, colour change or difficulty moving needs urgent assessment; fever may be absent. These selected examples do not cover every condition. Use appropriate local urgent or emergency services, including 911 for emergencies in the U.S. NHS back-pain guidance; NHS joint-infection guidance.
This is U.S. caregiver-written education, not individual medical, insurance, legal or financial advice. The operator is not a professional adviser. Your treating team assesses the clinical plan; the relevant provider, Medicare or plan clarifies coverage and payment questions. Cost, transport and fatigue barriers deserve discussion, but this guide does not choose visit frequency, exercise progression or a lower-cost treatment plan.
Table of Contents
Six essential checks for Medicare Part B physical therapy
| Check | Actual information to preserve | Question to clarify |
|---|---|---|
| 1. Coverage and setting | Original Medicare or exact Advantage plan; actual provider, setting, services and dates. | Which benefit and provider arrangements apply to this service? |
| 2. Explained skilled goal | Actual clinical goal and explanation of why therapist skills are needed. | Is the goal improvement, maintenance or slowing decline, and what skilled need was assessed? |
| 3. Certification status | Clinic answer about initial plan certification, relevant referral/order and later recertification. | Which route applies, what has actually occurred and what remains pending? |
| 4. Threshold process | Relevant year and actual billing-team tracking/KX or review explanation. | Which process is being discussed, and what does it establish about this claim? |
| 5. Estimate conditions | Included services, amount source, applicable deductible, other-payer information and actual notice. | What is confirmed, what changed and what remains unknown? |
| 6. Actual reply and owner | Question prepared or sent, real answer, scope and next action actually agreed. | Who will resolve each remaining clinical, billing or plan question? |
These are preparation prompts, not eligibility criteria or a pass score. A blank item can be the reason to ask for help. Record “not explained”, “not asked”, “reply pending” or “not confirmed” instead of filling the gap with an assumed approval. A complete record verifies none of the entries.
Identify the Medicare plan, service and actual setting
| Arrangement | Information to confirm | Assumption to avoid |
|---|---|---|
| Original Medicare outpatient PT | The actual outpatient service and setting, provider participation/assignment and applicable patient-cost conditions. | Every clinic, hospital or facility uses an identical total cost. |
| Medicare Advantage | Exact plan, actual service/location and the plan answer about network, authorization if required and cost-sharing. | Original Medicare cost examples automatically describe this plan. |
| Home health, SNF or inpatient rehabilitation | Which benefit and care arrangement the provider is actually proposing. | The word therapy makes a broader facility or home-health episode ordinary outpatient PT. |
| An additional or changed service | Which item, date, provider or location changed and whether the earlier answer still applies. | An answer for option A also verifies option B. |
The Medicare physical therapy coverage page describes medically necessary outpatient PT, certification and costs. Under Original Medicare, the general patient share is 20% of the Medicare-approved amount after the Part B deductible. Actual responsibility can also depend on other insurance, assignment and the setting. Keep these conditions attached to a quoted amount rather than applying a percentage to a clinic’s billed charge or cash price.
For an Advantage plan, obtain the actual plan’s answer instead of copying the Original Medicare illustration. A provider saying “we take Medicare” does not answer every network, service or payment question. Record the role, date and scope of the answer. No cost or authorization conclusion is produced by the organizer.
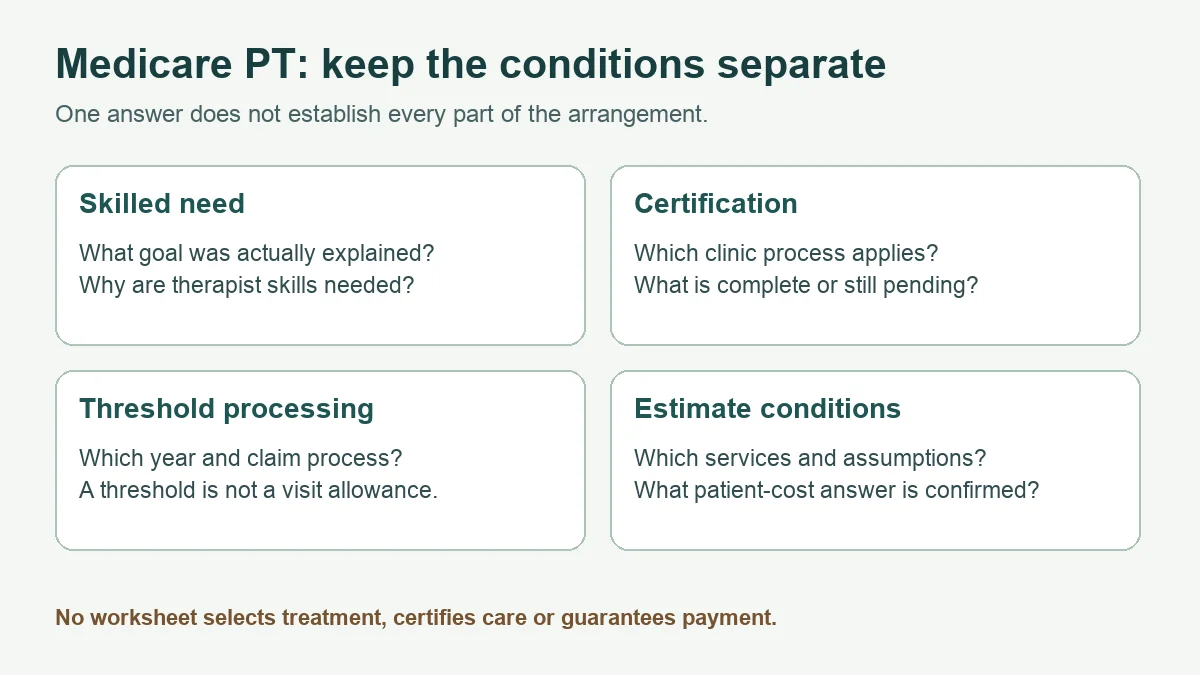
Keep skilled need distinct from improvement alone
A review should preserve the goal actually explained and the person’s pain, daily priorities and treatment burden. Improved function does not make ongoing pain unimportant. Equally, no perceived improvement does not by itself tell the reader that treatment is inappropriate, a claim must be denied or more visits are guaranteed.
CMS’s Jimmo guidance explains that coverage can include skilled therapy needed to maintain function or prevent or slow deterioration when therapist skills are necessary and other requirements are met. Coverage does not turn solely on the potential for improvement. Ask what skilled need was assessed in this situation; a maintenance label alone is not a personal coverage determination.
| What the person reports | Question for the treating team | Conclusion not established |
|---|---|---|
| Some improvement, but pain or burden remains | How does the mixed response relate to the explained goal and current needs? | Remaining pain should be dismissed or the same plan should automatically continue. |
| Progress has levelled off | What skilled need remains, and what is the actual goal and review plan? | Automatic discharge, automatic noncoverage or guaranteed continued coverage. |
| Maintenance or slowing decline was discussed | Which therapist skills are needed for the assessed plan? | Every maintenance activity requires covered skilled visits. |
| Cost, transport, fatigue or access is difficult | What clinically appropriate alternatives or support can address the actual barrier? | The reader should independently reduce visits or substitute a home program. |
Do not create an activity test or repeat therapy to prove a benefit, plateau or skilled need. Use existing observations and the relevant assessment. A financial estimate does not set clinical frequency. If instructions conflict or a proposed change is unclear, ask the treating team to reconcile the actual plan and record the answer. This guide supplies no continue/stop decision or recovery timetable.
Ask the clinic about certification and recertification
An order or referral, the therapist’s plan of care and certification are related but distinct records. Ask the clinic which applicable route it is using and what is actually complete. A referral sent or a future appointment booked does not, by itself, establish that all documentation requirements have been met.
CMS MLN905365, September 2025, pages 3–5 describes an initial-signature exception effective January 1, 2025. For certain therapist-established plans, a signed and dated physician/non-physician-practitioner order or referral on file can substitute when the specified conditions are met, including evidence the plan was delivered to that practitioner within 30 calendar days of the initial evaluation. The exception does not apply to recertifications or plans in a comprehensive outpatient rehabilitation facility (CORF). The clinic should check the actual conditions; this summary is not a compliance determination.
Record the real answer as “initial route explained”, “clinic confirmation received”, “clarification pending” or another accurate description. Keep later recertification separate. Do not treat the delivery interval as permission to delay care, a personal deadline calculated by the tool or a guarantee that a claim will pay. Billing and clinical teams can have different parts of the follow-through.
2026 thresholds, visit limits and patient cost are different
| Original Medicare outpatient therapy concept | 2026 rule or distinction | What it does not mean |
|---|---|---|
| Hard annual therapy cap | No hard annual payment cap for medically necessary outpatient therapy meeting the rules. | Every requested visit is automatically covered. |
| KX modifier threshold | PT and speech-language pathology (SLP) combined: $2,480; occupational therapy (OT) has a separate $2,480 threshold. | A personal bill, a visit allowance or an automatic stop point. |
| Targeted medical review threshold | PT/SLP: $3,000; OT separately: $3,000. Not every claim above it is reviewed. | An automatic denial or a universal prior-authorization rule. |
| Patient responsibility | Depends on applicable benefits, approved services, deductible and other coverage conditions. | The KX amount is what the patient must personally spend. |
CMS Therapy Services, CY 2026 gives the threshold amounts and explains that claims above the KX threshold require the modifier to confirm medical necessity supported by the record. Ask the billing team how applicable spending and claim processing are being tracked, including the PT/SLP combination. The organizer does not compute an accumulated balance or tell you whether to stop care. Confirm the relevant year before reusing an older answer.
Keep an actual threshold-processing answer separate from an authorization, a noncoverage notice and an estimate. Do not apply this table as an Advantage plan’s personal visit limit. A short note can say, “Threshold mentioned; which process, service period and actual claim status does that refer to?” That question is useful even without complete numbers.
Record estimate conditions, actual notices and real replies
| Record to obtain | Condition to preserve | Question to ask |
|---|---|---|
| Clinic estimate | Actual date, provider, setting, included services and assumptions. | What is included, excluded or changed from the previous version? |
| Medicare-approved or plan-allowed amount | Actual source and whether the number is confirmed or only an estimate. | Is this an approved/allowed amount, a full billed charge or something else? |
| Applicable deductible and other payer | Balance date, actual benefits answer and supplemental-payment uncertainty. | Which parts have actually been confirmed for these services? |
| Notice or decision | Exact title, issuer, dates, service scope and stated action or deadline. | Who can explain this actual document and its options? |
| Actual answer and next owner | Reply received with role/date/scope, remaining question and real agreement. | Who will act on the unresolved point, and what follow-up was agreed? |
A quote can change because its scope or assumptions changed. Ask what changed rather than assuming error or overcharging. For the arithmetic and estimate-to-EOB/bill comparison, the PT copay and coinsurance record has a different role. Here, first establish the Medicare-specific conditions and actual answers. Neither tool tells you what to pay.
CMS’s Original Medicare ABN information describes the Advance Beneficiary Notice of Noncoverage used in situations where payment is expected to be denied. An ABN is not an ordinary estimate or the final Medicare claim decision. If a notice is received, keep its actual wording and ask about the service, reason, costs, choices and applicable next steps. Do not assume every therapy episode needs an ABN or use this organizer to select an option or validate the notice. An Advantage plan notice needs its applicable plan process.
For any decision or notice, use its actual instructions and appropriate assistance. Do not replace a stated action or deadline with a general article rule, wait for this record to be complete or infer that sending a question extends a deadline. A question prepared, contact attempted, reply pending and answer received should remain separate statuses. The form sends nothing.

Two fictional writing examples
These are writing demonstrations, not patient cases, professional advice or coverage results. The example buttons replace current entries and label the brief fictional. No clinical assessment, approved payment, guaranteed number of visits or personal deadline is supplied.
Example A: progress levels off and skilled need needs clarification
| Record area | Fictional entry |
|---|---|
| Coverage / clinical question | Original Medicare outpatient PT discussed. Progress reportedly levelled off; ask what skilled need remains and what goal was actually assessed. |
| Plan / certification | No new home program or visit reduction supplied. Current certification and any recertification status are unconfirmed in the example. |
| Question / actual reply | Question prepared for the treating team and appropriate billing contact; not sent. No real clinical or coverage answer supplied. |
| Next owner | Record the actual assessment, clinic status and next action when agreed. A plateau alone establishes neither noncoverage nor continued approval. |
The note preserves uncertainty rather than treating improvement as a coverage test. It also does not assume skilled maintenance is the right plan. That requires the relevant individual assessment and all applicable coverage conditions.
Example B: threshold mentioned and an estimate changes
| Record area | Fictional entry |
|---|---|
| Scope | Confirm coverage type, setting, service period and included services before comparing the versions. |
| Threshold question | Threshold mentioned; actual yearly tracking and KX or review status unconfirmed. No personal threshold balance or visit allowance calculated. |
| Estimate / notice | Revised estimate received in this fictional example. Amount source, deductible and other-payer assumptions need clarification. No actual authorization or noncoverage decision supplied. |
| Actual contact / answer | Questions sent in this fictional example; replies pending. Record each real answer and its scope, without an approval, treatment or payment conclusion. |
The next task is to identify the changed condition and the person who can explain it, not automatically reduce visits or treat a threshold as the patient’s bill. A proposed financial or clinical change remains a proposal until the relevant answer or agreement is actually received.
Private Medicare PT conditions and actual-answer record
Download the offline tool before entering actual health or personal notes. Use fictional entries on this public page because the surrounding site may contain ads and analytics. The tool itself sends nothing, uses no browser storage and does not automatically save. The offline copy contains no external assets. Keep completed copies and exports private.
Use one service period or coverage discussion per record. If comparing several options, keep matching A/B labels in each field. Unknown, not asked and reply pending are useful entries. A paper note with the same headings works too. No new treatment trial or physical task is needed to fill this form.
Medicare PT plan, certification, threshold, estimate and actual-answer record
Follow one service period and its unanswered questions. Keep clinical need, certification, threshold processing, estimates and actual replies separate. Use matching A/B labels for multiple service questions.
Download the offline tool before entering actual health or personal notes. Use fictional entries here; the surrounding site may contain ads and analytics.
Offline copy. This file has no ads, analytics, external assets or automatic network requests.
The tool uses no network requests, browser storage or automatic saving. Refreshing or closing may lose entries. Keep exports private; omit names, identifying contact details and full records. Do not delay care for a record or routine reply.
Start with the fictional example or download a blank offline copy.
Paper alternative: Medicare type; setting/service; explained skilled goal; actual plan; certification status; threshold answer; estimate conditions; actual notice; questions; contact; actual answer; next owner. Unknown and pending are valid.
My Medicare PT plan, conditions and actual-answer record
Unverified personal record for discussion. Entries verify no plan, certification, threshold status, estimate, notice or coverage answer. No treatment change or payment decision is generated.
Guide: living.kioptrix.com/medicare-part-b-physical-therapy/
Blank fields generate optional questions, not a failure score. Every entry remains unverified even if all fields contain text. Rebuild after editing, then copy, download text or print the brief. Exporting does not contact Medicare, certify a plan, add a claim modifier, appeal a decision or send a clinical instruction.
Common Medicare PT questions
Does a plateau automatically end Medicare PT coverage?
No. Ask about the assessed skilled need and actual goal. Maintenance can qualify under the applicable requirements, but the organizer cannot establish continued coverage.
Does crossing a threshold tell me how much I owe?
No. Threshold processing and personal cost-sharing are different. Ask about the actual claim process and estimate conditions separately.
Is an order the same as completed certification?
Do not assume that. Ask the clinic which valid route applies and what it has actually completed, keeping recertification separate.
Can I use a cost example to reduce therapy visits?
This page selects no treatment frequency. Raise the actual cost or access barrier with the treating team and ask about clinically appropriate alternatives or support.
Does a full record verify my benefits?
No. It records unverified notes and questions. Actual professional answers, documents and their scope remain necessary; a complete form establishes no approval or amount to pay.
Sources, corrections and review limits
- Medicare: Physical therapy services — Original Medicare outpatient PT eligibility and cost context.
- CMS: Jimmo Settlement — skilled maintenance and the absence of an improvement-only standard; other conditions still apply.
- CMS MLN905365, September 2025, pages 3–5 — certification, the initial-signature exception and its limits.
- CMS: Therapy Services, CY 2026 — annual KX amounts and targeted review distinction.
- CMS: FFS ABN — Original Medicare noncoverage-notice context; not a personal notice determination.
- NHS: Back pain and NHS: Septic arthritis — selected symptom warnings, not U.S. coverage rules. Use local care routes.
Source check and editorial update: October 29, 2026. Replaced the long generic pain-and-cost narrative with Medicare-specific conditions and actual-answer tracking. Removed treatment-frequency selection cards, budget-led trimming advice, the unattributed caregiver anecdote and improvement-only implications. The original URL, publication date, author and classification are retained.
This is selected education, not a systematic evidence review, individual coverage determination or validated clinical instrument. No independent clinical/Medicare-specialist review, real-reader usability study or improved outcome is claimed. The hero is AI-generated fictional artwork; diagrams explain separate records and roles. Our background and editorial approach.