

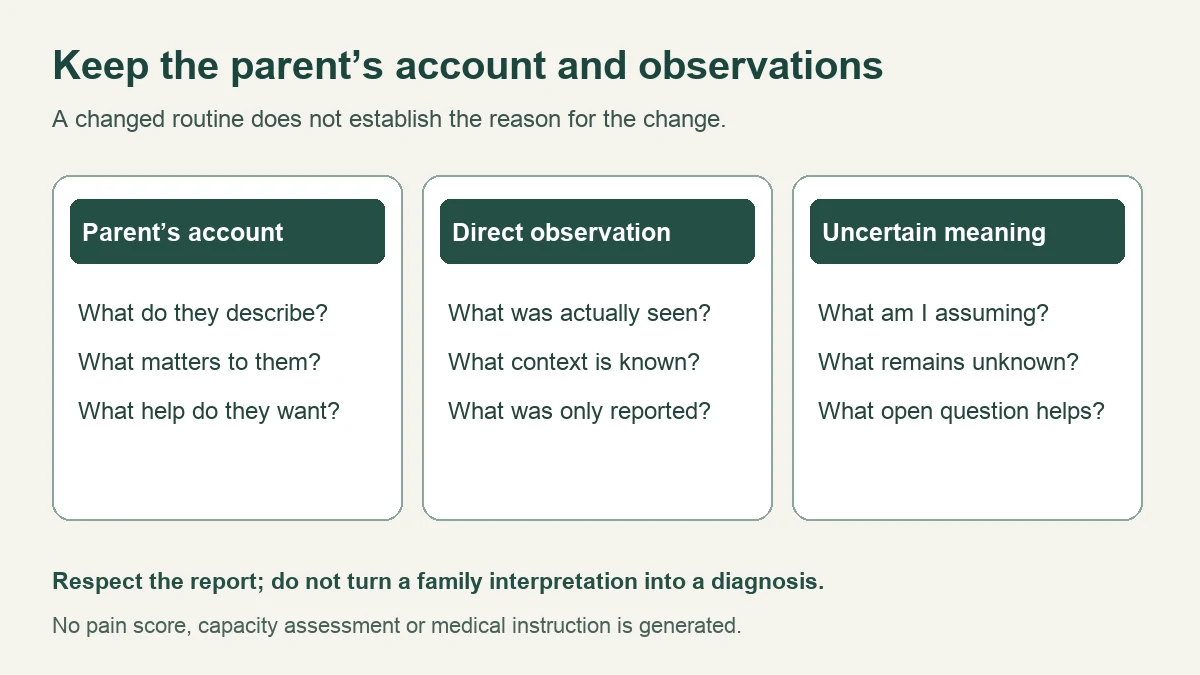
Helping an older parent with orthopedic pain starts with their account, not a family explanation of what they “really mean.” A parent may describe pain as unchanged while a relative notices fewer outings. Keep both accounts, ask what is still unclear, and agree what help is wanted. Neither visible activity nor a family worry cancels the parent’s pain report.
Use the account–observation–interpretation comparison, follow seven essential support checks, read two fictional writing examples, or download the free offline conversation and support record. Begin with one concern; no symptom test or diary period is required.
This guide focuses on everyday conversations when an older parent’s explanation, a helper’s observations and practical support do not yet line up. The separate orthopedic visit with a parent guide covers participation at a specific appointment. This page connects the everyday question to the actual clinical answer and assistance really delivered.
This is U.S.-focused general education from a family-caregiver-run website. The operator is not a medical or legal professional. No independent clinical review, clinical validation of the record or assessment of a reader’s family arrangement is claimed. The form does not determine decision-making ability, urgency, safe time alone or adequate care.
Table of Contents
Needed assessment comes before a family conversation record
Call local emergency services for chest pain, serious breathing difficulty, inability to wake normally, new confusion, stroke-like symptoms, major injury or another serious acute problem. In a U.S. emergency call 911. These are selected examples from MedlinePlus emergency guidance, not a complete triage checklist. Do not wait for a family agreement, completed worksheet or routine callback.
Severe hip pain after an injury, inability to walk or bear weight, or tingling/loss of feeling after injury needs emergency assessment. Do not test walking. Sudden severe hip pain without injury or a hot, swollen hip needs urgent advice; a joint infection can occur without fever. See NHS hip-pain warnings and septic-arthritis guidance. Back pain with new bladder/bowel changes, saddle-area numbness or symptoms in both legs needs emergency assessment; see NHS back-pain warnings. UK sources provide symptom education, not U.S. service instructions.
Report a fall or concerning change to the appropriate care team. CDC advises prompt medical review after a head impact in an older adult, particularly with medicines such as blood thinners; see CDC fall facts. Medicine errors or new medicine-related concerns need medicine-specific advice. Severe symptoms take the emergency route. This page sets no observation interval and does not require the parent to prove difficulty before receiving care.
Orthopedic pain: separate the parent’s account from family interpretation
An unfinished chore, missed outing or changed routine is an observation worth discussing, not a diagnosis. There may be pain, another concern, a practical barrier or a preference; the reason has not been established from the observation alone. Ask rather than announcing that the parent is hiding pain or losing independence.
| Information type | Example of a clear record | What it does not establish |
|---|---|---|
| Parent’s account | “My pain feels about the same. I want to discuss my sleep.” | That pain is mild, that nothing changed or that family observations are irrelevant. |
| Direct observation | “I noticed fewer outings. I do not know the reason.” | That pain caused the change, or that the parent is concealing it. |
| Helper interpretation | “I wondered whether discomfort affected going out.” | A clinical finding, diagnosis or more truthful account than the parent’s. |
| Open question | “What influenced going out less, and is there anything you want help with?” | Consent to change medicines, devices, routines or who receives information. |
| Actual clinical explanation | The real professional reply, source and scope, or “not yet received.” | An explanation assumed from message receipt, a family theory or an earlier diagnosis. |
IASP pain terminology treats pain as a personal experience and emphasizes respecting the person’s report. It also recognizes that communication difficulty does not rule out pain. Activity observations can supplement the conversation; they are not a pain detector. This is terminology guidance, not a condition- or procedure-specific care plan.
Seven essential checks for parent-led orthopedic pain support
Retain the parent’s own concern
Ask what they want explained or helped with. Record their words about pain, sleep, comfort, worries and daily life without selecting function as the most legitimate concern. A completed task does not disprove pain; a missed task does not explain its cause.
Describe observations without mind-reading
State what was directly seen and distinguish it from something another person reported. Use context already known. There is no need to repeat stairs, walk a route, delay a shower or reproduce pain for a clearer record. Leave the cause uncertain when it is uncertain.
Ask what help and sharing are wanted
Ask about notes, calls, task assistance and who may hear the relevant information. Record help declined without automatically calling the parent resistant. Participation support and appropriate representation may need professional guidance; age or disagreement is not a home test of decision-making ability.
Keep current instructions and unanswered points
Retain actual advice and its source if known. A proposed change is not an instruction. Conflicting medicine, activity, device or care instructions need clarification from the relevant team; the family worksheet does not choose between them or invent an interim treatment.
Separate contact from an actual clinical answer
Keep the question, actual recipient role and real reply together. A message sent, administrative acknowledgement or family answer is not automatically individualized clinical advice. Write “not received” rather than assuming permission, reassurance or a diagnosis.
Confirm support someone really accepted
Ask which specific task a helper accepted, its limits and actual availability. A willing relative, a named sibling or a proposed service is not proof of accepted responsibility. If the help requires appropriate assessment or teaching, ask the relevant professionals what is needed.
Record what happened and the gap still open
Note assistance actually delivered and agreed changes actually implemented. Preserve partial help alongside unmet needs. Identify the real next owner if agreed; leave that unknown otherwise. No promise, sent message or family calendar entry proves that the care gap is resolved.
Ask open questions about orthopedic pain without ranking concerns
An orthopedic pain conversation can include pain intensity, comfort, sleep, feelings, daily tasks and support needs. Do not require a functional loss before taking pain seriously or insist on a pain score before asking for help. If a question is difficult to answer, ask what communication support would help rather than filling in an explanation on the person’s behalf.
| Instead of assuming | Try an open question | Record the remaining uncertainty |
|---|---|---|
| “You skipped the shower because you are afraid.” | “What influenced postponing it, and would you like any help?” | Reason and wanted assistance may still be unknown. |
| “You say fine, but your walking proves otherwise.” | “What does fine mean for you today? Is there a concern you want addressed?” | Keep the parent’s explanation and observed change together. |
| “The medicine made you unsteady.” | “What did you notice, what was actually used, and what should we ask the clinician or pharmacist?” | Timing alone does not establish the cause. |
| “We should move everything and try it for a week.” | “What concern needs review, which change is proposed, and whose guidance is needed?” | No route trial, treatment experiment or fixed waiting period is supplied. |
Choose a manageable starting question if helpful, but do not make “one small change first” a rule before professional assistance. A current care need may require several arrangements or assessment now. The parent does not need to be calm, rested or ready for a long conversation before urgent care can be sought.
If the conversation becomes difficult, separate disagreement about an explanation from an immediate care concern. Appropriate professional advice may help clarify support or representation. This guide does not authorize a relative to declare incapacity, override a choice or replace a needed assessment with a family vote.
Compare orthopedic pain support wanted, accepted and provided
| Stage | What to confirm | What remains separate |
|---|---|---|
| Parent’s preference | What help is wanted, declined or still undecided. | A family preference or assumed permission. |
| Proposed arrangement | Which task or service is being discussed and any known conditions. | A confirmed visit, service start or accepted responsibility. |
| Actual acceptance | Who really agreed, to which task and with what limits. | Clinical advice or assistance already provided. |
| Actual provision | What help happened, who supplied it and what did not happen. | A promise, scheduled event or assumption of improved safety. |
| Actual answer / remaining owner | Real professional advice, remaining question and accepted next step if known. | An inferred response, safe waiting time or resolved care need. |
Keep the parent’s preferences central without assuming that every family member can supply the needed help. A remote check-in may be useful while physical assistance remains absent. An offered ride may not include help inside the home. Record that scope directly rather than marking all support complete because somebody responded.
CDC care-plan guidance supports planning with the person receiving care, organizing current care information, updating after changes and respecting privacy. It also discusses continuity when caregivers change. It does not validate this worksheet or establish that a particular family arrangement meets an individual’s needs.
For medicine questions during orthopedic pain care, retain the actual product and instructions in private records and ask the clinician or pharmacist about concerns. NIA medicine-safety guidance supports accurate medicine information and professional review; it does not set a dose or correction for this parent. No medicine schedule or exercise limit is supplied here. For an equipment question, AAOS walking-aid guidance provides general use information, not personal fit or clearance from this article.
Family involvement, permission to receive information and authority to decide are different. HHS family-and-friends guidance describes circumstances for relevant sharing; being an adult child does not create blanket access. Ask the service which arrangements apply. The tool records preferences and actual arrangements without granting legal authority.

Two fictional writing examples: different accounts and undelivered help
These are invented writing examples, not actual family stories, medical advice or verified outcomes. No diagnosis, treatment change or safe waiting time is supplied. They show how to preserve uncertainty and incomplete support. Needed care comes before a fuller note.
Example A: pain feels unchanged, but outings have decreased
| Record | Fictional entry |
|---|---|
| Parent account | “Pain feels about the same.” The parent wants their own explanation retained. |
| Direct observation | A relative noticed fewer outings; the reason has not been established. |
| Interpretation / permission | The relative wondered whether pain contributed. The parent agrees to a short private question to the team. |
| Contact / actual clinical answer | A question is drafted. Sending, receipt and a clinical reply are not claimed. |
| Support / open issue | No new support or benefit is established. The reason and wanted assistance remain questions. |
A note could say: “My parent reports unchanged pain. I noticed fewer outings but do not know why. They agree to discussing both accounts. What needs clarification, and what support do they want?” This does not translate “unchanged” into denial or replace the account with a diagnosis.
Example B: assistance was accepted but not delivered
| Record | Fictional entry |
|---|---|
| Parent preference | The parent wants assistance with an already identified daily task. |
| Accepted responsibility | A family helper reportedly accepted the task. Scope and availability need clarification. |
| Actual provision | The assistance was not supplied. No unsafe attempt alone is requested. |
| Reply / clinical answer | A family reply acknowledges the gap. No individual clinical answer is supplied. |
| Unresolved need | Who can address the current need and what actual plan applies remain open. No successful resolution is claimed. |
A note could say: “This help was wanted and accepted, but it did not happen. The parent’s need remains. Who has accepted responsibility for addressing the gap, what advice actually applies, and what support is really available?” Do not record the parent as refusing help when the problem is failed provision.
Private parent conversation, actual-answer and support record
Download the offline tool before entering actual health or care details. Use fictional entries on this webpage because surrounding advertisements and analytics may be present. The tool itself makes no network requests, uses no browser storage and does not automatically save. The offline copy contains no external assets or automatic network requests.
Start with one concern. Blank items produce optional questions rather than scores or clinical instructions. Omit names, addresses, private contacts, identifiers, access details, label photographs and full medical reports. Use the agreed private route and relevant information only. Paper with the same headings works; a complete record is never a condition for care.
Parent conversation, actual answer and support record
Begin with one concern. Any field may remain blank; optional questions are generated without scoring the parent or prescribing a next treatment.
Download the offline tool before entering actual health or care details. Use fictional entries here; surrounding ads and analytics may be present.
Offline copy. No ads, analytics, external assets or automatic network requests.
The tool makes no network requests, uses no browser storage and does not save automatically. Refreshing may lose entries. Omit names, addresses, private contacts, identifiers and full reports. Needed care comes before this record.
Start with the fictional example or download a blank offline copy.
Paper alternative: parent account; observation; interpretation; permission; current instructions; contact; actual clinical answer; accepted support; help delivered; remaining gap and owner.
My parent conversation, actual answer and support record
Unverified personal record for discussion. Entries verify no diagnosis, advice, completed change or treatment outcome.
Guide: living.kioptrix.com/orthopedic-pain-management-5/
Build the record, then copy, download text or print/save PDF. Editing hides the previous output until rebuilt. The two example buttons replace entries and mark the output fictional. Offline exports contain current entries, so keep completed copies private. Closing or refreshing can lose unsaved notes. Nothing is sent to a clinician or helper by the tool.
Where this parent orthopedic pain guide fits
This page addresses everyday differences between the parent’s account, family observations and actual support. For participation in a specific orthopedic appointment, use the companion guide. For home recovery tasks and actual care provision, use the home-support guide. This article does not duplicate their full appointment or discharge checklists.
The point is not to gather evidence against a parent’s account. It is to preserve their concern, make an uncertain interpretation visible, get the relevant actual answer and check that wanted assistance really happened. A family-caregiver perspective can help organize that conversation, but it cannot substitute for an individual clinical explanation.
Common questions about helping a parent with orthopedic pain
Should I believe the pain report or the change I noticed?
Keep both without ranking one as the truth. Respect the parent’s report, describe the observation and ask what remains unclear. Neither establishes the cause of the other.
Does refusing one offer mean my parent refuses all help?
No. Record the particular help declined, what the parent says and any alternative wanted. Do not use the worksheet to judge decision-making ability or delay necessary advice.
Must we complete a week of notes first?
No. There is no minimum diary, waiting period, pain score or function threshold in this guide. Needed assessment and assistance come first.
Does a message acknowledgement settle the question?
Only the actual content and role tell you what was answered. Receipt alone does not supply individualized clinical advice or complete practical help.
Can a family member speak or access records automatically?
No blanket authority comes from the relationship or this form. Ask about the parent’s preferences and actual service arrangements; obtain appropriate guidance when participation or representation is uncertain.
Can this record establish that living alone is safe?
No. It has no clinical risk score, capacity assessment or support-adequacy test. It keeps the real help and unresolved gaps visible for an appropriate discussion.
Sources, corrections and review limits
Editorial revision and source check: October 30, 2026. This version replaces interpretations of “fine” and unfinished tasks as hidden pain, function-first comparisons, numeric snapshot fields, fixed trial/diary periods and the unverified chair story. It removes the generic treatment routine, unrelated video and duplicated artwork. The older targeted-update note is replaced by this revision scope.
- IASP pain terminology — personal experience and respectful reporting; not condition- or procedure-specific advice.
- CDC care-plan guidance — participation, current records, updating and privacy; not clinical validation of this tool.
- CDC older-adult fall facts — U.S. fall risks and post-fall concerns; not a diagnosis from changed habits.
- NIA taking medicines safely as you age and AAOS walking-aid guidance — general medicine review and device education; not individual dose, fit or movement instructions.
- HHS family-and-friends information — relevant information-sharing circumstances; not authority created by this worksheet.
- MedlinePlus emergency guidance and NHS hip pain, joint infection and back-pain warnings — selected symptom examples; not a complete triage assessment or universal service pathway.
The seven checks, comparisons and tool are editorial communication aids. No independent medical review, professional assessment of a reader’s support, user-outcome study or validated decision instrument is claimed. The representative image is an AI-generated fictional parent–daughter conversation; it is not a real assessment or proof of a care outcome. The two diagrams illustrate information and responsibility distinctions. Independent qualified review and reader usability research would strengthen the resource.