
This site is written from a family-caregiver perspective. The operator is not a medical professional or an insurance, legal or financial adviser. Use this guide to organize questions for the relevant service.
Check the scan, interpretation and plan credit
- Keep together
Actual MRI order, contrast status, site, scan and interpretation quotes and report-delivery arrangement.
- Question to resolve
Will a cash payment count under this plan, and who bills for interpretation or added services?
- Next contact and action
Confirm the complete transaction before paying. Discuss protocol changes with the ordering team; a lower cash quote may not mean a lower total annual cost.
- Follow-up record
Record the date, office or representative, reference number, answer received, unanswered question, next owner and agreed review date. Recheck when the care plan, notice, provider, benefits or circumstances change. Keep identifying details in your private records.
HealthCare.gov HDHP definition
Editorial update: October 22, 2026. This update adds a topic-specific follow-up record and removes unsupported personal anecdotes. The existing guide remains below; this is not a complete clinical, legal, tax or coverage review.

The cheapest MRI is the one that arrives in one envelope
When you’re staring at lumbar MRI cost with a high-deductible plan (HDHP), the system loves to hand you three confident numbers that don’t match: facility fee vs professional fee, “allowed amount” vs self-pay bundle, with contrast vs without. Meanwhile, your back hurts—sometimes in that familiar nerve-pain down-the-leg way—and your deductible clock keeps ticking.
Keep guessing and you can lose hundreds (sometimes more), burn your HSA, or delay the scan until the problem—and the price—gets worse.
This guide helps you get a real all-in quote (scan + interpretation), lock the CPT code so your comparisons are fair, and choose cash-pay vs insurance with a simple deductible rule—plus the questions that prevent “surprise” fees and prior auth headaches.
Everything here is built from real phone-call friction and the exact mistakes that create second bills.
Get the one number.
Then compare like an operator.
- Secure an all-in cash bundle (including the radiologist read)
- Match CPT + contrast status across facilities
- Decide what’s cheapest for your deductible year
- Schedule without getting ambushed later
Table of Contents
Lumbar MRI cost: Who this is for / not for
If you’re here, you probably have two tabs open: one for your back pain, and one for your bank account. This guide is for the person stuck in that exact split-screen life—trying to be responsible without becoming a full-time billing detective.
For: HDHP members paying mostly out-of-pocket (for now)
- You haven’t met your deductible yet (or you’re not close).
- You can choose between facilities (hospital outpatient vs imaging center).
- You want a quote that includes the radiologist read.
- You’re willing to make 3 calls to save real money.
Not for: “don’t wait” scenarios (symptoms + timelines)
- New bladder/bowel control problems.
- Rapidly worsening weakness, numbness, or saddle-area numbness.
- Severe pain with fever, recent major trauma, or cancer history concerns.
- You’re being told “today or ER” by a clinician.
- Start with “all-in price” (scan + read).
- Then lock CPT + contrast status across quotes.
- Only then compare facilities.
Apply in 60 seconds: Find your order and circle “with contrast / without / with & without.” That single phrase changes everything.
Money Block: 60-second eligibility checklist (Yes/No)
Answer honestly. A single “No” doesn’t end the plan—it tells you what to ask next.
- Yes/No: I can choose the facility (not locked to one hospital system).
- Yes/No: My doctor’s order is clear on contrast (or I can clarify).
- Yes/No: I can wait a few days if the cheapest slot isn’t tomorrow.
- Yes/No: I’m comfortable making 3 quick calls.
- Yes/No: I’m willing to request “scan + read” as one number.
Neutral next step: If you answered “No” to facility choice, skip negotiation and focus on claim strategy + getting the read included.
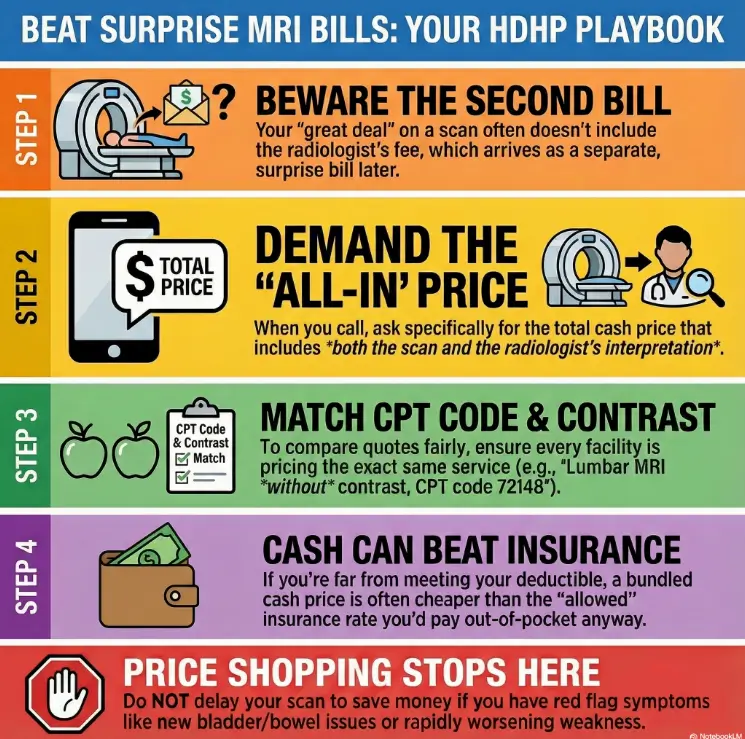
Lumbar MRI cost: The HDHP pricing illusion (why cash can win)
Here’s the weird truth: on an HDHP before you meet your deductible, “using insurance” often feels like paying retail—but with extra steps. That’s not you being dramatic. That’s the math of allowed amounts, facility pricing, and who’s holding the steering wheel during the transaction.
The three price layers you’re quoted (and which one matters today)
- Chargemaster/list price: the sticker price. Almost nobody pays this, but it haunts estimates like a ghost story.
- Insurance-negotiated (allowed) amount: what your plan says is “reasonable.” On an unmet deductible, that can still be big.
- Cash/self-pay bundle: a simplified “pay today” number some facilities use to avoid claims friction and collections risk.
That’s the illusion: you assume in-network = cheapest. But before deductible, you’re basically paying the allowed amount anyway—so a clean cash bundle can undercut it.
Open loop: “If I pay cash, am I throwing away deductible credit?”
Not always, but you can accidentally do that. Some self-pay transactions never touch your insurance record unless you submit paperwork (or the facility agrees to file). And even when you submit, the plan can treat it differently depending on network rules, prior authorization, and documentation. We’ll handle this with a decision rule and a clean “ask before paying” script.
Operator mindset: Don’t compare “cheap vs expensive.” Compare “cheap that counts” vs “cheap that becomes two bills later.”
Cash quote: The one-number script (scan + read, all-in)
Request written expected charges for the scan and interpretation, identifying each billing entity and any excluded items. If you are not using insurance, CMS says you can usually request a Good Faith Estimate. Estimates can cover only one provider or facility, so request the radiologist’s estimate separately when needed. A quote is not automatically a guaranteed single bill.
Ask for one total (not five partial totals)
Copy/paste phone script (cash quote):
“Hi—I’m scheduling a lumbar spine MRI. I’m on a high-deductible plan and may self-pay. Can you quote me the all-in cash price for the MRI including the radiologist interpretation? I also need the CPT code you’ll bill, and whether it’s with contrast, without contrast, or with-and-without. Finally, how fast is the report turnaround—24 hours, 48 hours, or longer?”
Confirm what’s included: radiologist read, facility fee, report delivery
- Radiologist read included? If yes, ask: “Is that guaranteed as one bill or two?”
- Images + report delivery: portal access, CD/USB, or electronic transfer to your doctor.
- Any add-ons: sedation, extra series, contrast materials, or “STAT” fees.
Pattern interrupt: Let’s be painfully clear—if they can’t give an all-in number, you’re not comparing prices. You’re collecting suspense.
Money Block: Quote-prep list (bring this to every call)
- Your doctor’s order (lumbar spine; contrast status; diagnosis code if listed).
- Your plan basics: deductible remaining, coinsurance %, and whether imaging needs prior authorization.
- Whether you need same-week results (work, travel, pain management timeline).
- Preferred days/times (so you don’t pick the pricey place just because it’s “soon”).
- One question you will not forget: “Does the quote include the radiologist interpretation?”
Neutral next step: Put your deductible remaining and coinsurance in a note on your phone. That turns “maybe” decisions into clean math later.
Another small truth: the person answering the phone is usually not trying to trick you. They’re juggling scheduling software, billing vocab, and your anxiety. Your job is to be calm and specific. Their job is to give you the code and the total. Team sport.
CPT codes: The landmines that break every quote
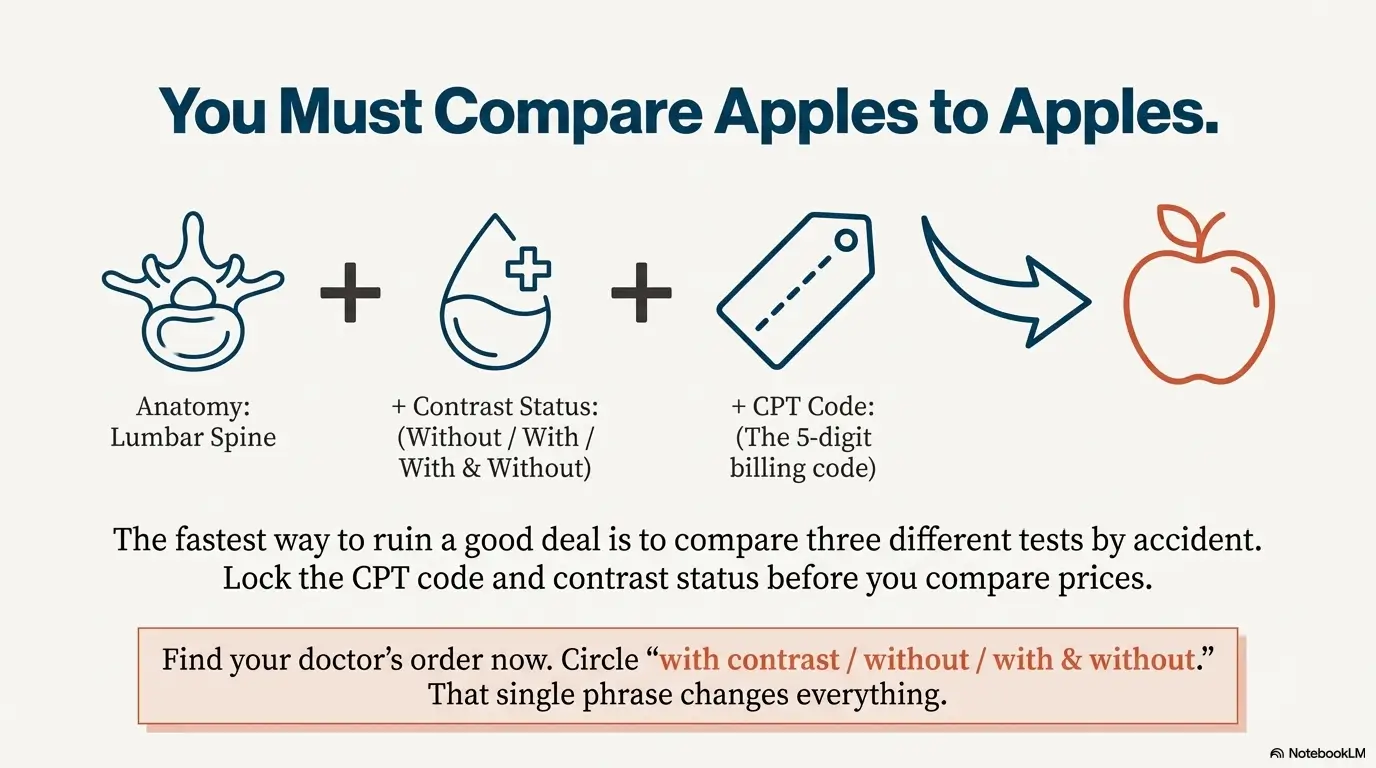
The fastest way to ruin a good deal is to compare three different tests by accident. CPT codes (the billing codes maintained by the American Medical Association) and contrast status can turn “same MRI” into “different universe.” You’re not being picky—you’re protecting yourself from a mismatched quote.
Contrast fork: without vs with vs with/without (and what your order says)
- Without contrast: common for many lumbar spine questions.
- With contrast: may be used for certain post-op questions, infection/tumor concerns, or specific clinical scenarios.
- With and without contrast: two-part imaging; often costs more and takes longer.
Practical tip: if your order says “with and without,” don’t assume they’ll “decide later.” Ask if the order can be clarified by your clinician. Otherwise you may get quoted for one thing and billed for another.
Add-ons that show up later (sedation, extra views, images transfer, second read)
- Sedation: may trigger extra monitoring and facility charges.
- Contrast materials: can change the total quote.
- Image transfer: some places charge for physical media or expedited requests.
- Second opinion reads: sometimes worth it, but ask the price up front.
Open loop: “Can contrast be decided mid-scan—and repriced?”
Sometimes a radiologist may recommend contrast after seeing initial images, but the facility should have a protocol. If that happens, ask two things: (1) “Will you stop and get authorization from my ordering clinician?” and (2) “What is the cash price difference if we add contrast today?” If they can’t answer, you’re signing up for a number you never agreed to.
Show me the nerdy details
“Quote integrity” is basically a three-variable system: anatomy (lumbar) + contrast status + setting (hospital outpatient vs freestanding). Change any one and you changed the product. Your goal isn’t to learn billing trivia—your goal is to prevent a facility from saying “Oh, that quote was for a different code” after the scan is done.
Money Block: Quote tracker table (fill-in)
Write down exactly what each place says. This keeps you from “remembering the cheapest number” that didn’t include the read.
| Year | Facility | CPT + Contrast | All-in cash range ($___–$___) | Notes (read included? turnaround?) |
|---|---|---|---|---|
| 2025 | Center A | _____ / _____ | $___–$___ | _____ |
| 2025 | Center B | _____ / _____ | $___–$___ | _____ |
| 2025 | Hospital outpatient | _____ / _____ | $___–$___ | _____ |
Neutral next step: If any cell is blank, call back and fill it. Missing info is how surprises breed.
Deductible math: Cash pay vs insurance (a decision rule)
For a same-visit comparison, obtain the complete cash quote and the insurer’s estimated patient responsibility for the same facility, radiologist, code, and contrast status. Deductible remaining alone cannot establish which is cheaper: the covered allowed amount, coinsurance, copays, out-of-pocket limit, and claim rules matter. HealthCare.gov explains deductibles.
If you’re far from deductible: when cash usually wins
If you’re early in the year (or you rarely use healthcare), cash can win because it’s a clean, discounted bundle. The “insurance route” often makes you pay the plan’s allowed amount until you hit the deductible anyway. Cash doesn’t guarantee savings—but it often gives you control and a fixed number.
If you’re near deductible / expect more care: when insurance can win
If you expect multiple visits, facet steroid injections vs longer-lasting options, physical therapy for chronic low back pain, or other imaging, a claim that counts toward deductible can be valuable. Paying cash for a big service can feel good today and hurt later if you end up meeting your deductible anyway.
Pattern interrupt: Here’s what no one tells you—your “insurance price” estimate is often a moving target until the claim processes. Your out-of-pocket can still end up higher than you expected if pieces bill separately. That’s why “scan + read” matters so much.
Money Block: Mini calculator (cash vs insurance path)
Assumes a covered in-network service subject to one deductible, then coinsurance. It excludes copays, out-of-pocket caps, separate provider deductibles, noncovered charges, and later care. Enter a combined allowed amount only if the same rules apply to scan and read. Otherwise request the insurer’s itemized estimate.
Enter your numbers, then click Compare.
Neutral next step: Use this output to decide which phone call you make next: insurer estimate or cash quote follow-up.
- If you’re far from deductible, cash bundles can often win.
- If you’re near deductible and expect more care, counting can win.
- Either way, “scan + read” is non-negotiable.
Apply in 60 seconds: Write your deductible remaining on paper. That number is the hinge of your decision.
Prior auth: The paradox that can erase savings
Prior authorization is the administrative boulder that can roll downhill onto your savings plan. Even if you self-pay, prior auth can still matter if you want the scan to count toward deductible, or if your ordering clinic or facility refuses to proceed without it. The paradox: you’re trying to simplify, but the system tries to complicate.
When pre-auth still matters (even if you self-pay)
- You want to submit to insurance after paying (or want it to count).
- Your doctor’s office is sending the order through an insurance workflow.
- The facility requires prior auth to protect themselves from denials and disputes.
If you want it to count: what to ask before you schedule
Ask these three questions (word-for-word):
- “If I self-pay, will you still submit a claim to my insurance, or provide a superbill for me to submit?”
- “Do you require prior authorization before you’ll perform the scan?”
- “Will the radiologist interpretation be billed together, or separately?”
Open loop: “Can I pay cash and file later?”
Filing after self-payment depends on both the provider’s agreement and the plan’s rules. Confirm network status, timely-filing deadlines, required authorization, claim forms, and whether choosing a no-claim cash rate prevents later submission. Get insurer confirmation before paying; a superbill is not a promise of reimbursement or deductible credit.
Show me the nerdy details
Think of prior auth as the plan’s “permission slip.” The permission slip is tied to a code, a place, and a reason. If any of those change (new CPT, new facility, new contrast status), the permission slip can become useless. That’s why you lock the CPT and location when you request an insurer estimate.
One more human detail: if you’re in pain, admin tasks feel twice as heavy. That’s why your goal isn’t “perfect compliance.” Your goal is “no surprises.” A clean all-in quote plus clear filing expectations gets you most of the way there.
Facility choice: Hospital outpatient vs imaging center (where savings live)
This is where the biggest price spread tends to hide: the setting. Many people default to the hospital because it feels “official.” But hospital outpatient departments often carry facility overhead that freestanding imaging centers simply don’t. That doesn’t automatically make hospitals bad—it just means you should compare with open eyes.
The usual ladder: hospital outpatient vs freestanding center
- Hospital outpatient: convenient inside a health system; often more expensive; sometimes faster scheduling for complex cases.
- Freestanding imaging center: often competitive cash pricing; sometimes quicker for routine MRIs; varies widely by ownership and staffing.
Quality checks that cost $0 (scanner type, report turnaround, redo policy)
- Scanner details: ask “Is it wide-bore? Do you have an open MRI option?” (comfort matters for motion-free images).
- Turnaround: “When will the report be ready?” Get a specific timeframe.
- Redo policy: “If images are unreadable due to motion, do you redo at no charge?”
“Cheap but slow” trap: when delays create second-order costs
If the cheapest place can’t deliver the report for a week and your clinician needs it to decide treatment, that delay can cost you time, work days, and extra appointments. A slightly higher price with a 24–48 hour report can be the real bargain—especially if you’re in the “how long can I wait?” zone for herniated disc sciatica wait time decisions.
Show me the nerdy details
Motion is the enemy of MRI clarity. Better comfort (wide-bore, clear instructions, a calm tech) can reduce motion artifacts and lower the chance of repeats. That’s not luxury—it’s risk control. Ask how they coach patients through the scan and whether they allow music or ear protection options.
Negotiation: What actually works (and what wastes time)
Negotiation doesn’t have to be awkward. Think of it as asking for the pricing policy that already exists—but isn’t always offered unless you ask. You’re not begging. You’re clarifying.
Prompt-pay discount, competitor match, bundled read (the 3 asks)
- Prompt-pay: “If I pay today in full, is there a self-pay discount?”
- Competitor match: “Another center quoted $X all-in including the read—can you match that?”
- Bundled read: “Can you guarantee the radiologist interpretation is included in the all-in amount?”
HSA/FSA payments + receipts: what to request at checkout
If you’re using an HSA, you’ll want clean documentation. The IRS explains HSAs in Publication 969, and the practical takeaway is simple: keep itemized receipts and documentation that ties the expense to medical care. Ask the facility for a receipt showing what service was provided and the date of service.
Don’t do this: arguing list price or asking “lowest possible”
- Don’t argue the chargemaster/list price. It’s rarely the real lever.
- Don’t ask “What’s the lowest you can do?” Ask for a specific policy: self-pay bundle, prompt-pay discount, or match.
- Don’t negotiate without CPT + contrast status locked.
- Use one number: scan + read.
- Use one reference: competitor all-in quote.
- Use one condition: pay in full today.
Apply in 60 seconds: Text yourself the best quote you’ve gotten so far, including “read included.” That becomes your matching tool.
Personal aside: the first time I asked for a prompt-pay discount, my voice did that little nervous squeak. The scheduler didn’t flinch. They just said, “Yes, we have a self-pay rate.” I felt silly for waiting years to ask.

Common mistakes: The 9 ways HDHP patients overpay
This section is the guardrail. It’s the part you skim, nod, and then avoid stepping off the cliff anyway—unless you keep it open while you make calls. (Yes, I’m speaking from experience.)
Mistake 1: Booking before confirming “read included”
If the quote doesn’t include the radiologist interpretation, you don’t have a quote—you have a fragment.
Mistake 2: Not matching CPT + contrast across quotes
Different code = different product. Lock it.
Mistake 3: Assuming in-network = lowest out-of-pocket
On an unmet deductible, “in-network” can still be expensive. Compare all-in cash.
Mistake 4: Paying cash without asking about claim filing/superbill
If you want it to count, confirm filing rules before you pay.
Mistake 5: Ignoring turnaround time (then paying twice elsewhere)
Cheap plus slow can become “cheap + second MRI.”
Mistake 6: Forgetting that hospital outpatient bills can be multi-part
Facility and professional fees can show up separately. Sometimes even more pieces.
Mistake 7: Not asking how results are delivered
Your clinician needs the report and/or image access. Confirm the method.
Mistake 8: Over-tightening your schedule instead of widening your options
If you can shift by 1–3 days, you may unlock better pricing and faster reporting elsewhere.
Mistake 9: Shopping forever (and never scanning)
At some point, the “best price” becomes the enemy of “getting answers.”
Don’t delay: When to seek help (price shopping stops here)
This is the safety gate. Cost optimization is useful—until it isn’t. If you’re dealing with red flags or rapid changes, the correct move is speed, not savings. Your future self will thank you for acting like your symptoms matter more than a discount.
Red flags (don’t wait for a cheaper slot)
- New trouble controlling bladder or bowels.
- Numbness in the groin/saddle area, or rapidly worsening leg weakness.
- Severe pain with fever, chills, or recent serious infection.
- Recent major trauma, or symptoms that escalate hour by hour.
Neutral next step: New bladder/bowel dysfunction, saddle numbness, or severe/rapidly worsening weakness requires emergency care now. Other concerning symptoms need urgent clinical assessment; do not delay for price shopping.
If symptoms worsen while waiting: the “switch plans” rule (go now, shop later)
If you booked a low-cost slot but your symptoms are getting worse, don’t cling to the plan like it’s a moral achievement. Switch to the earliest clinically appropriate option. The point of shopping is to reduce waste—not to delay needed care.
FAQ
Is a lumbar MRI cheaper with cash pay on an HDHP?
It can be, especially before you meet your deductible. The key is getting an all-in cash bundle that includes the radiologist interpretation and matching CPT + contrast status across quotes.
Will a cash-pay MRI count toward my deductible?
Do not assume a cash payment will count. Before paying, ask your insurer whether this specific self-pay arrangement can be submitted, which allowed amount or payment receives credit, and which deductible/out-of-pocket accumulator applies. A receipt or superbill alone does not guarantee credit. Also confirm the facility’s claim-filing terms.
Do I need prior authorization if I’m paying cash?
You may. Some facilities require it, and it can matter if you want the service to count toward your insurance tracking. Ask both your plan and the facility what they require for your specific order and location.
What’s the difference between facility fee and professional (radiologist) fee?
The facility fee covers the scanner, staff, and site overhead. The professional fee covers the radiologist’s interpretation. Either can be billed separately unless you secure an all-in quote.
Why are hospital outpatient MRIs usually more expensive?
Hospital outpatient departments often have different overhead and billing structures than freestanding centers. That doesn’t mean hospitals are “bad”—it means you should compare total cost, turnaround, and how results are delivered.
What should I ask to get an apples-to-apples quote?
Ask for: (1) the all-in total including radiologist read, (2) the CPT code, (3) contrast status, and (4) report turnaround time.
Next step: The 3-calls + 1-call plan (done in 30 minutes)
This is the part where you stop reading and start saving. You don’t need a spreadsheet empire. You need four calls and a place to write down answers. Put a timer on if you like—it helps keep the process from swelling into a whole afternoon.
Call 3 centers: collect total cash price + CPT + contrast + turnaround
- Call a freestanding imaging center near you.
- Call a second freestanding center (or a different network).
- Call the hospital outpatient department (if it’s an option).
Ask for the all-in cash number including the radiologist read, CPT + contrast status, and report turnaround. If anyone hesitates, repeat calmly: “I’m comparing facilities and need the all-in total including the read.”
Call insurer once: request patient-responsibility estimate for the same CPT + facility
Then call your insurer and request a patient-responsibility estimate for the same CPT code at the specific facility. Use the facility’s legal name if you have it. Keep it simple and specific.
Money Block: Decision card (Cash vs Insurance)
Choose cash pay when:
- You’re far from meeting the deductible.
- You can get a true all-in bundle (scan + read).
- You need a fixed number and fast scheduling.
Choose insurance path when:
- You’re close to meeting the deductible or expect more care soon.
- Your plan requires prior auth and you want it to count cleanly.
- You’ve confirmed how the radiologist fee will be billed.
Neutral next step: Pick the path that minimizes total year cost, then schedule the appointment you’ll actually attend.
Infographic: The HDHP MRI “No-Surprise” Flow
1) Lock the product
CPT code + contrast status + lumbar spine.
2) Get one number
All-in cash quote: scan + radiologist read.
3) Check counting
Will they file? Do you need prior auth?
4) Choose the win
Lowest total year cost + report timing that works.
One more lived detail: the best plan is the plan you can execute while tired and in pain. If this feels like too much, do the smallest version—call two centers instead of three. Progress beats perfection.
Conclusion
Let’s close the loop from the hook: yes, you can often cut a lumbar MRI bill on an HDHP—sometimes dramatically—without becoming a billing expert. The seven wins are simple, repeatable, and frankly a little boring: lock the CPT + contrast status, demand the all-in price including the read, compare facility settings, protect deductible counting when it matters, and stop shopping when symptoms say “now.”
If you have 15 minutes, do this: pick three places, use the script, and write down the one-number totals. Then make one insurer call for the patient-responsibility estimate on the exact same CPT and facility. That’s how you turn anxiety into a decision.
And if you’re reading this while uncomfortable, genuinely: be gentle with yourself. The system is confusing on purpose. You’re not failing—you’re navigating.
Updated: October 14, 2026